This information is for research and educational purposes only. No medical recommendations. Products are not approved for human use. For health questions, consult a doctor.

Lexicon

Rosuvastatin (Crestor)

The most potent approved statin - stronger per milligram and far less prone to interactions.

3 min read 7 sources

Molecule model of glossy blue, light blue and white spheres with one pale yellow sphere, floating above a white podium with a glowing rim in a bright lab, symbolic image for rosuvastatin
Compound approved · since 2003

Summary

At a glance

Sources checked on 26 Oct 2026

Major vascular events (JUPITER)
−44 %

17,802 people without raised LDL but with raised CRP, against placebo, stopped after a median of 1.9 years1

Cardiovascular events (HOPE-3)
−24 %

12,705 people at intermediate risk without cardiovascular disease, median 5.6 years2

LDL in JUPITER
−50 %

CRP fell by 37 percent1

Half-life
~19 hours

about 90 percent of the effect comes from the compound itself, not from breakdown products5

  • Rosuvastatin is a statin. It inhibits HMG-CoA reductase in the liver, the liver cells then pull more LDL out of the blood.75
  • In JUPITER major vascular events fell by 44 percent in people without raised LDL but with raised CRP. The trial was stopped after a median of 1.9 years. In HOPE-3 there were 24 percent fewer events at intermediate risk.12
  • On ultrasound of the coronary arteries plaque regressed on the highest study dose (ASTEROID). Against the highest atorvastatin dose there was no clear difference in the main measure (SATURN).34
  • Only about 10 percent of rosuvastatin is metabolised, according to the label CYP3A4 plays no relevant role. Muscle complaints and a slightly higher diabetes risk are the known points.51
  • According to ChEMBL rosuvastatin has been approved since 2003. Everything here is the state of research, not a recommendation.7
Profile

Updated July 2026

How long does it stay in the body?

Share left after one dose, calculated with a half-life of ~19 hours

Half-life ~19 hours
After 38 hours: 25 %
Hour 19 · 50 %Hour 24, next dose · 42 %Hour 38 · 25 %Hour 57 · 12.5 %Hour 95 · 3.1 %

Simplified model without an absorption phase, half-life from the TPD lexicon.

Class
Statin

HMG-CoA reductase inhibitor

Use
Oral

once daily, time of day irrelevant

Half-life
about 19 hours
Metabolism
Mostly excreted unchanged

barely any CYP3A4

Potency
Clearly stronger per milligram than atorvastatin
Contents 12 sections
  1. At a glance
  2. What is rosuvastatin?
  3. How it works
  4. Use and dosing
  5. What the research shows
  6. Research status
  7. Side effects
  8. Storage
  9. Related compounds
  10. FAQ
  11. Glossary
  12. Sources

What is rosuvastatin?

Rosuvastatin is the most potent approved statin. It inhibits the same HMG-CoA reductase as atorvastatin but binds more strongly and for longer. In practice that means: at the same milligram figure it lowers LDL more.

The second difference is pharmacokinetic and at least as important day to day: rosuvastatin is barely metabolised through CYP3A4 and is mostly excreted unchanged. Anyone taking other substances that run through that enzyme has considerably fewer conflicts here.

This information is for research and educational purposes only. No medical advice.

Comparison

Three paths to less LDL

Statins, bempedoic acid and ezetimibe act at different points, as stated in the TPD lexicon. Tap a card to open its entry.

Simplified: statins and bempedoic acid slow cholesterol production in the liver, ezetimibe its uptake in the gut. 7

How it works

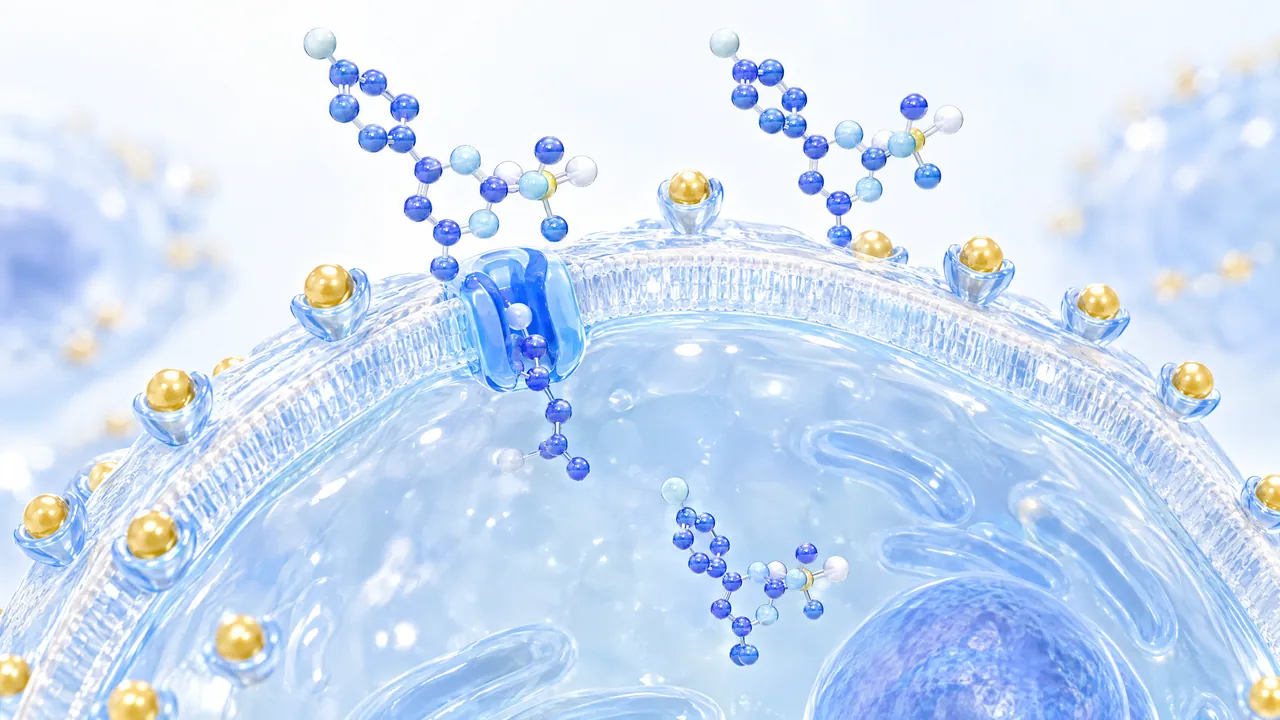
Rosuvastatin is hydrophilic, meaning water-soluble. It enters the liver cell through a dedicated transporter rather than simply diffusing through any cell membrane. That is part of why the muscle burden is comparatively favourable relative to its potency.

With a half-life of around 19 hours the time of day does not matter, unlike with the short-acting statins. A fixed time still helps, simply so the dose does not get forgotten.

A point that often gets lost: in people of East Asian ancestry plasma levels average roughly twice those in Europeans, which is why lower starting doses are used there. That is not a footnote, it is stated in the prescribing information.

Where it acts

Where rosuvastatin acted in studies

Tap a point or a card. Colour = HMG-CoA reductase, grey = observed in studies.

  1. Liver

    Inhibits cholesterol production, more LDL receptors on the liver cell7

    HMGCR
  2. Blood lipids

    LDL lowered by 50 percent, CRP by 37 percent (JUPITER)1

    Observed in trials
  3. Heart

    24 percent fewer cardiovascular events against placebo (HOPE-3)2

    Observed in trials
  4. Brain

    Fewer strokes, 0.18 instead of 0.34 per 100 person-years (JUPITER)1

    Observed in trials
  5. Muscle

    Muscle pain 7.6 versus 6.6 percent, rarely muscle breakdown5

    Observed in trials
  6. Kidney

    Protein and blood in the urine described as laboratory findings5

    Observed in trials

Targets in the ChEMBL database7

Compound CHEMBL1744447: one recorded mechanism, Inhibitor, direct binding.
HMG-CoA reductase
Gene
HMGCR
UniProt
P04035
ChEMBL
CHEMBL402
Action
Inhibitor, direct binding
Section of a glassy blue cell with a nucleus, golden spheres in small cups along the membrane, blue molecule chains pass through a blue channel in the membrane into the interior
Rosuvastatin enters the liver cell through a transporter. Symbolic image.

Use and dosing

Dosing

Dosing, titration and syringe

Loading the dosing information …

  • Getting started and stepping up, drawn as a staircase
  • Units on the U-100 syringe for every step
  • How long one vial lasts
White folding box with the TPD logo next to a blister of ten round white tablets, two loose tablets in front on a bright lab bench
Tablets in a blister. Symbolic image.

What the research shows

JUPITER (NEJM 2008) is the best known and most debated trial. Almost 18,000 people without elevated LDL but with elevated CRP as an inflammation marker received 20mg rosuvastatin or placebo. The trial was stopped after barely two years: the primary combined endpoint fell by 44 percent. The main criticism was that the absolute event rate was low, which makes the relative figure look more impressive than the absolute benefit.

HOPE-3 (NEJM 2016) tested the same idea at intermediate risk without prior disease and found 24 percent fewer events. ASTEROID (JAMA 2006) showed on intravascular ultrasound that existing plaque actually regresses under 40mg, rather than merely growing more slowly.

SATURN (NEJM 2011) compared rosuvastatin 40mg directly with atorvastatin 80mg. Both regressed plaque. On the primary ultrasound measure there was no significant difference between them. Rosuvastatin achieved a lower LDL in the process, which raises the question of how tightly the LDL number and plaque regression are really coupled.

Study results

What the trials measured

Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.

Fewer events without known heart disease12

Relative risk reduction of the primary outcome against placebo, values from the abstracts

JUPITER1 Infarction, stroke, vessel procedure, unstable angina, cardiac death
Rosuvastatin -44%
HOPE-32 Cardiac death, infarction or stroke
Rosuvastatin -24%

Calculated from the hazard ratios 0.56 and 0.76. In JUPITER the event rate was 0.77 instead of 1.36 per 100 person-years, so the absolute difference is small.

Share with a cardiovascular event2

12,705 people at intermediate risk, median 5.6 years

Cardiac death, infarction, stroke2
Placebo 4.8%
Rosuvastatin 3.7%
Plus procedures, heart failure, resuscitation2
Placebo 5.7%
Rosuvastatin 4.4%

LDL was on average 26.5 percent lower on rosuvastatin than on placebo. The results pointed the same way across risk groups, lipids, CRP and ethnic origin.

Change in plaque share of the vessel34

Percent atheroma volume after 24 months or 104 weeks, highest study doses

ASTEROID3 349 evaluable people, no comparison group
Rosuvastatin -0.98 pp
SATURN4 1,039 people, head-to-head
Atorvastatin, highest dose -0.99 pp
Rosuvastatin -1.22 pp

The difference in SATURN was not significant (p = 0.17). LDL was 1.62 instead of 1.82 mmol/l on rosuvastatin, on total atheroma volume rosuvastatin did better.

Transparent glass tube that opens from a narrow point into a wide section, light blue lines of light flowing through it
In ASTEROID and SATURN plaque in the vessel regressed. Symbolic image.

Research status

Where the research stands

Rosuvastatin has been approved since 2003. On ClinicalTrials.gov 904 trials list rosuvastatin among their interventions, often as a comparator. Shown are the registered trials from this entry. As of 26 Oct 2026. 6

  1. Preclinical Principle: inhibition of HMG-CoA reductase in the liver
  2. Phase 1 no registered trial
  3. Phase 2 no registered trial
  4. Phase 3 3 trials, 2 completed, 1 stopped early
  5. Approval since 2003
20,585 participants in phase 3 Approved: ChEMBL lists rosuvastatin with phase 4 as the highest phase and first approval in 2003.7
Show all 4 phase 3 and 4 trials on a timelineHide timeline 3 completed 0 running 1 stopped early 4 with results
Phase 3
Phase 4

Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026, grey = stopped early.

Side effects

  • Muscle pain: possible as with all statins. Anyone training hard has elevated CK anyway. New, unfamiliar muscle pain on a statin needs checking.
  • Protein in urine: described at 40mg, usually transient and without disease significance, but the reason for caution with the maximum dose.
  • Liver values: small rises common, clear rises need checking.
  • Blood sugar: slightly raised risk of new-onset diabetes, as with the whole class.

Tolerability

Side effects compared with placebo

Frequency in the two large placebo-controlled trials, JUPITER over a mean of 2 years, HOPE-3 over a median of 5.6 years.

7 of 100 Placebo
8 of 100 Rosuvastatin
Event PlaceboRosuvastatin
Muscle pain (JUPITER)5 7%8%
Joint pain (JUPITER)5 3%4%
New diabetes (JUPITER)5 2%3%
Muscle symptoms (HOPE-3)2 5%6%
Cataract surgery (HOPE-3)2 3%4%

In HOPE-3 there was no excess of diabetes or cancer. Among laboratory findings the label lists protein and blood in the urine as well as, rarely, muscle breakdown (rhabdomyolysis).25

Storage

Store dry, at room temperature and protected from light. Keep out of reach of children.

Three white tablet bottles on a bright shelf next to a folded light blue towel
Dry, at room temperature and away from light. Symbolic image.
Level · Rosuvastatin (Crestor)

How the level builds up

One dose per day: each dose adds to what is left of the previous one.

Lexicon: Oral, once daily, time of day irrelevant
Peak 1.71×Trough 0.71×
Day 3 · 4. dose
1.66× of the first dose
Plateau
from Day 3

97 % of the plateau after dose 4

Peak
1.71×

of the first dose

Trough
0.71×

before the next dose

Simplified model, values relative to the first dose, no dosing information. Dashed: the first dose alone, green: the plateau.

Related

Related compounds

Same targets or a different path: all in the TPD lexicon.

FAQ

Common questions about Rosuvastatin (Crestor)

Short answers, each backed by the sources below.

How does rosuvastatin lower LDL?

It inhibits HMG-CoA reductase, the key enzyme of cholesterol production in the liver. The liver cell then puts more LDL receptors on its surface and pulls more LDL out of the blood. According to the label the maximum LDL reduction is usually reached after 4 weeks, the half-life is about 19 hours.75

Is rosuvastatin approved?

Yes. ChEMBL lists rosuvastatin as an approved compound with first approval in 2003. On ClinicalTrials.gov 904 trials list rosuvastatin among their interventions (as of 26 October 2026). Everything here is the state of research, not a recommendation.76

What did JUPITER show and why is it debated?

17,802 apparently healthy people with normal LDL but raised CRP received rosuvastatin or placebo. After a median of 1.9 years the trial was stopped: 0.77 instead of 1.36 events per 100 person-years, so 44 percent fewer. The relative figure is large, but the absolute difference per year is small because the overall event rate was low.1

Can plaque regress?

In ASTEROID the plaque share of the vessel fell on average by 0.98 percentage points after 24 months on the highest study dose of 40 mg, LDL fell by 53.2 percent. In SATURN both rosuvastatin and the highest atorvastatin dose regressed plaque, without a clear difference in the main measure.34

What about interactions?

Only about 10 percent of rosuvastatin is metabolised, according to the label its clearance does not depend on CYP3A4 to a relevant extent. Instead it uses transporters such as OATP1B1. Drugs that inhibit these transporters, such as ciclosporin or certain HIV drugs, raise the level considerably.5

Why does ancestry matter?

According to the label the level in people of Asian ancestry is about twice as high in the median as in a white comparison group. With severely reduced kidney function it rises to about three times.5

What about muscles and blood sugar?

In JUPITER 7.6 percent had muscle pain on rosuvastatin and 6.6 percent on placebo. New diabetes was reported in 2.8 instead of 2.3 percent, HbA1c rose by 0.1 percentage points on average. In HOPE-3 there was no excess of diabetes, but slightly more muscle symptoms.52

Glossary

Terms explained briefly

Dotted words in the text open these explanations directly.

Atheroma volume
Amount of plaque in the vessel wall, measured by ultrasound from the inside. The percentage share is the strictest measure of it.
CRP
C-reactive protein, an inflammation marker in the blood. In JUPITER a raised level was the condition for taking part.
CYP3A4
Liver enzyme that breaks down many compounds. If something inhibits it, the level of other drugs rises.
Hazard ratio
Ratio of the event rate of two groups over time. 0.56 means 44 percent fewer events.
HMG-CoA reductase
Enzyme in the liver that controls the slowest step of the body's own cholesterol production.
Hydrophilic
Water-soluble. Such substances pass less easily through cell walls on their own and rather need transporters.
LDL
Cholesterol carrier in the blood. High levels are closely linked to deposits in the vessels.
OATP1B1
Transporter that carries rosuvastatin from the blood into the liver cell.
Person-years
Sum of the observation time of all participants. 100 person-years are about 100 people over one year.
Rhabdomyolysis
Severe breakdown of muscle tissue that can strain the kidneys. Rare on statins.
Statin
A group of compounds that inhibit the key enzyme of cholesterol production and so lower LDL.

Evidence

Sources

Show all 7 sourcesHide sources 4 Studies1 Trial registry2 Database checked 26 Oct 2026

Studies

  1. JUPITER: rosuvastatin with raised CRP without raised LDL

    Ridker et al., New England Journal of Medicine, 2008

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  2. HOPE-3: cholesterol lowering at intermediate risk

    Yusuf et al., New England Journal of Medicine, 2016

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  3. ASTEROID: plaque regression on ultrasound

    Nissen et al., JAMA, 2006

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  4. SATURN: rosuvastatin versus atorvastatin in plaque comparison

    Nicholls et al., New England Journal of Medicine, 2011

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed

Trial registry

  1. Trials on rosuvastatin on ClinicalTrials.gov

    ClinicalTrials.gov, U.S. National Library of Medicine

    Checked 26 Oct 2026 via ClinicalTrials.gov API v2

Database

  1. US prescribing information for rosuvastatin

    DailyMed, U.S. National Library of Medicine (Stand 19.01.2026)

    Checked 26 Oct 2026 via DailyMed, openFDA
  2. Mechanism and approval in ChEMBL

    ChEMBL, EMBL-EBI (CHEMBL1496, Mechanismus am Calciumsalz CHEMBL1744447)

    Checked 26 Oct 2026 via ChEMBL


