What is Orexin B?
Orexin B, also called hypocretin-2, is a 28-amino-acid neuropeptide. It is cut from the same precursor protein as orexin A and is made by a small group of neurons in the lateral hypothalamus. These neurons act like a switch for wakefulness and arousal: active when you are awake and alert, quiet during sleep.
The orexin system was discovered in 1998 by Sakurai and colleagues, originally in the context of food intake regulation - hence the name ("orexis" is Greek for appetite). It quickly became clear that the much bigger role lies in sleep-wake regulation. In humans, loss of these orexin neurons is the core mechanism behind narcolepsy type 1.
One thing up front that runs through this whole entry: orexin B is a pure research peptide. It is not a medicine and has not been studied for human use - least of all as a subcutaneous injection. This information is for research and educational purposes only. No medical recommendations.
Comparison
Orexin B and other wake and sleep topics in the lexicon
Entries in the TPD lexicon around wakefulness and sleep. Tap a card to open its entry.
The entries act in different ways, only the topic is compared here.
How it works
Orexin B binds to orexin receptors, of which there are two: OX1R and OX2R. Orexin B is clearly selective for OX2R - its affinity for OX1R is roughly 10 to 100-fold lower. That OX2R is tightly linked to sleep-wake control, while OX1R is more associated with motivation, reward and autonomic functions.
Through OX2R, orexin neurons activate downstream wake-promoting systems in the brain and stabilize the awake state. When orexins are missing, that switch flips uncontrollably - that is the model behind narcolepsy. The logical research idea: if orexin deficiency causes sleepiness, then OX2R agonism might do the opposite and promote wakefulness. That is exactly why orexin receptor agonism is researched for wakefulness and narcolepsy.
The crucial catch is in the next section: for orexin B to do anything in the brain, it first has to get there. And with peripheral dosing, that is the problem.
Where it acts
Where orexin B acts
Tap a point or a card. Colour = receptor, grey = observed. All from animal and cell studies.
Known targets4
Compound PubChem CID 44404987: two described targets, type of action on each card.
- Gene
- HCRTR2
- UniProt
- O43614
- ChEMBL
- CHEMBL4792
- Action
- Agonist, as strong as orexin A
- Gene
- HCRTR1
- UniProt
- O43613
- ChEMBL
- CHEMBL5113
- Action
- Agonist, 10 to 100 times weaker than orexin A
What you need
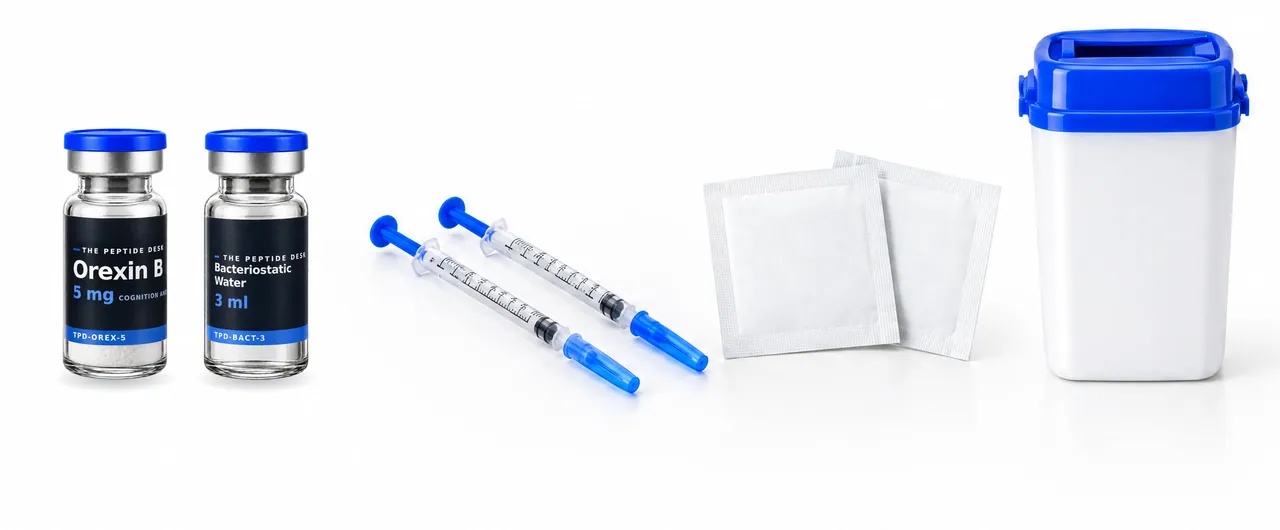
Before you start, have everything ready:
Supplies
5 things, numbered as in the picture
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-
Orexin B vial
The orexin B vial with the freeze-dried powder
-
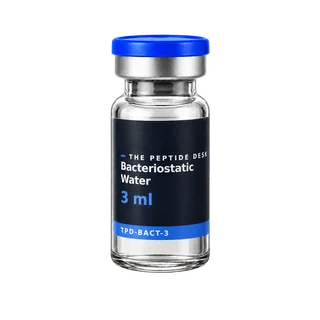
Bacteriostatic water
Bacteriostatic water for reconstitution
-
U-100 insulin syringes
U-100 insulin syringes for administration
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin site
-
Sharps container
A sealable container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
Orexin B is a fragile peptide. Be careful when reconstituting and storing it, or you will end up with nothing but expensive water in the vial.
Reconstitution
The powder is dissolved with bacteriostatic water. How much water you use sets the concentration. That determines how many units you draw on the insulin syringe for your dose. When dissolving, just add the BAC water, it does not matter if it hits the powder directly. Then swirl or shake until everything has dissolved, both are fine.
Use the peptide calculator for exactly this: pick the vial size and water volume to see the concentration and the units per dose right away.
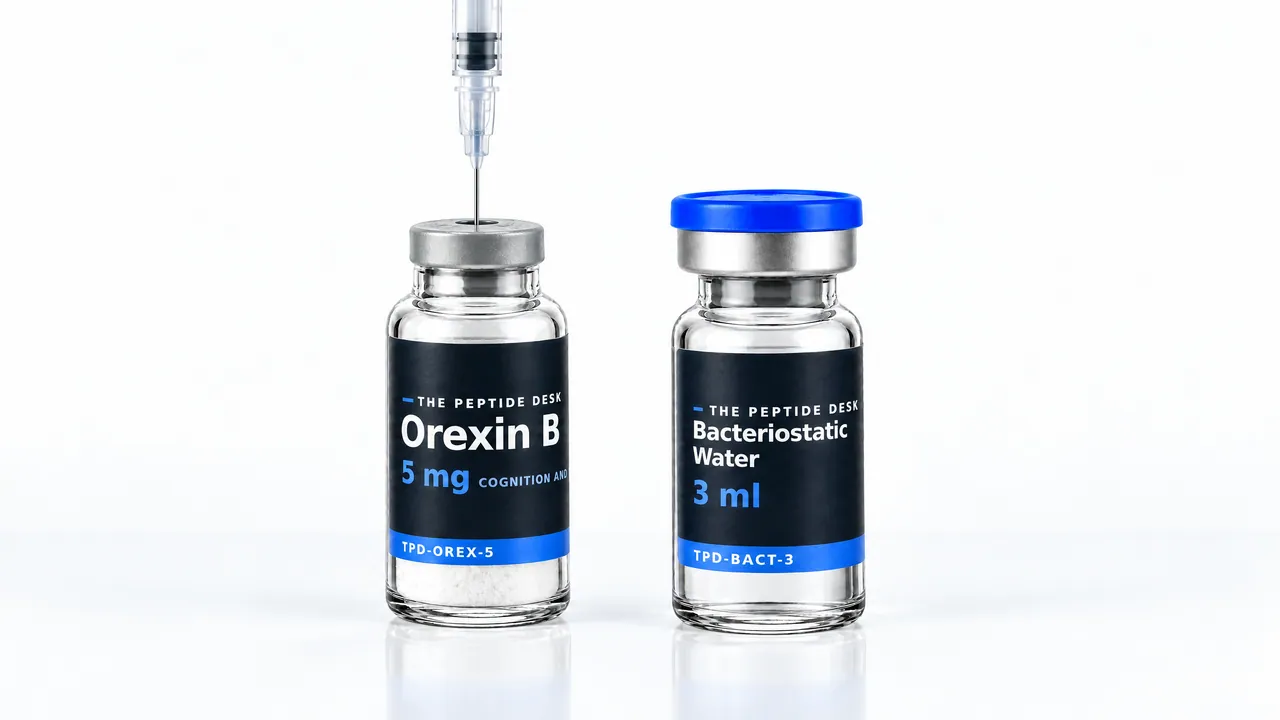
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
Injection is subcutaneous, into the fatty tissue under the skin. Typical sites are the abdomen (avoiding the area right around the navel), the front and the inner side of the thigh, or the back of the upper arm.
Injection
Where and at what angle
Pick a spot or switch the angle. Subcutaneous means: into the fat layer, not the muscle.
Rotate the spot each time, never the same one twice in a row.
Rule of thumb: where there is more fat under the skin, insert straight at 90 degrees. In lean people with little fat, 45 degrees, so the needle stays in the fat layer. Simplified diagram.
-
Clean the skin site with an alcohol swab and let it dry
-
Pinch up a small skin fold
-
Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
-
Inject slowly, wait briefly, then withdraw the needle
-
Drop the needle straight into the sharps container
Rotate the injection site every time. But honestly: even a perfect subcutaneous injection leaves the central effect doubtful - the reason is right below.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
Most of what is known about orexin B comes from cell systems and animal models, not humans:
- Discovery and appetite: In a rat model, centrally administered orexin increased food intake. During fasting the peptide was upregulated (Sakurai 1998, preclinical).
- Blood-brain barrier: In mice, orexin A crossed the barrier by simple diffusion, whereas orexin B was rapidly degraded in blood and did not reach the brain intact (Kastin & Akerstrom 1999, preclinical). This is the central reality check for peripheral dosing.
- Receptor role: Reviews clearly assign OX2R, orexin B's preferred receptor, to sleep-wake control (Sun, Tisdale & Kilduff 2021).
- Narcolepsy context: Loss of orexin neurons is considered the core mechanism of narcolepsy type 1 - this supplies the logic for why orexin agonism is researched for wakefulness at all (Kornum et al. 2017).
What is missing matters just as much: there is no solid human data for peripherally injected orexin B as a wake-promoting or metabolic peptide.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
How lipid-soluble the two orexins are3
Octanol/buffer partition coefficient, higher means more lipid-soluble and easier passage through the blood-brain barrier
Values according to the abstract (0.232 and 0.030). In mice orexin A entered the brain from the blood quickly and mostly intact. Orexin B was broken down so fast in the blood that no intact orexin B could be detected in the brain.
What is missing in the orexin system in narcolepsy78
Share in percent, the body's own orexin, not injected orexin B
7 of 9 equals 77.8 percent. For the nerve cells the study gives a range of 85 to 95 percent, the chart shows the lower value. The cells for the hormone MCH next to them were not reduced. This shows why the orexin system is researched for wakefulness, not that injected orexin B works.

Research status
Where the research stands
The registry lists many trials of drugs that block or stimulate orexin receptors. There is no trial with the peptide orexin B as the compound. As of 26 Oct 2026. 9
- Preclinical Animal studies and cell systems
- Phase 1 no registered trial
- Phase 2 no registered trial
- Phase 3 no registered trial
- Approval not yet
So far there is no registered trial in humans. 9
Side effects
Again: there is no established side-effect profile for peripherally administered orexin B in humans, simply because the application has not been studied.
- Local reactions at the injection site (redness, swelling, mild irritation) are conceivable with any subcutaneous peptide
- Since the orexin system is linked to arousal, cardiovascular function and appetite, effects on wakefulness, circulation or hunger cannot theoretically be ruled out - described in the research context, not proven for this route
- Purity and correct reconstitution are critical: poorly dissolved or contaminated material is a risk in its own right
The absence of documented side effects is not proof of safety, it is a sign of missing data.
Context
Orexin B is one of those peptides where the theory sounds more exciting than the practice delivers. The OX2R signal is real and linked to wakefulness, that is well established. The sticking point is delivery: as a subcutaneous injection, orexin B barely reaches the brain because it is degraded too fast in blood. For a central wake effect, the peripheral injection is probably the wrong route.
Treat orexin B as what it is: an experimental research peptide with thin human data, whose peripheral benefit is open to doubtful. Anyone who wants realistic expectations should factor that in honestly.
Storage
The undissolved powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. Once mixed, it keeps for at least 4 to 6 months in the fridge (2 to 8 °C). The bacteriostatic water carries a preservative that keeps the dissolved form stable longer. Protect from light and heat. Avoid repeated freeze-thaw cycles.
Shelf life
How long it keeps
Robust, no fridge needed. Keeps for several months without trouble.
Keeps for at least 4 to 6 months. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial