


What is Triptorelin?
Triptorelin is a synthetic decapeptide modeled on the body's own gonadotropin-releasing hormone (GnRH). Unlike many compounds in the research space, triptorelin is an actually approved drug: under brand names like Decapeptyl or Trelstar it has been used in medicine for decades, including in prostate cancer, endometriosis and precocious puberty. So there is plenty of human data here - a rare and welcome starting point.
The crucial thing about triptorelin is that the same substance does two completely opposite things depending on how it is used. A single dose acts as a short push on the hormone axis. Continuous, ongoing dosing (depot) does the exact opposite after a few weeks: it powers the axis down. Confuse the two and you misunderstand the substance entirely.
This information is provided solely for research and educational purposes. No medical recommendations.
Comparison
Four points on the hormone axis
Where the entries from the TPD lexicon act on the axis of brain, pituitary and testes. Tap a card to open its entry.
Simplified: triptorelin and gonadorelin hit the same receptor. With continuous dosing triptorelin shuts the axis down, a short pulse stimulates it. 75
How it works
Triptorelin binds to the GnRH receptors in the pituitary gland - the same receptors that the body's own pulsatile GnRH normally drives. What happens next depends entirely on the timing pattern of dosing:
- First dose (flare): The pituitary is stimulated and releases a burst of LH and FSH. That drives the gonads to produce more testosterone or estradiol. This acute rise is well documented in studies and is even used deliberately in reproductive medicine to trigger an LH surge.
- Continuous dosing (suppression): With continuous, non-pulsatile occupation of the receptors, the pituitary responds with downregulation and desensitization. After typically 2 to 4 weeks, LH and FSH collapse and gonadal hormone production drops to the floor. This exact effect is used in prostate cancer, where the goal is to push testosterone down to castration levels.
That is the core: a pulse pushes, continuous bombardment switches off. In prostate cancer use, the initial flare phase is actually a known problem because the short testosterone rise can temporarily worsen the disease (so-called tumor flare) - the FDA label warns about this explicitly.
Where it acts
Where triptorelin acts
Tap a point or a card. Colour = GnRH receptor, grey = observed in studies.
Targets in the ChEMBL database7
Compound CHEMBL1201334: one recorded mechanism, Agonist (ChEMBL).
- Gene
- GNRHR
- UniProt
- P30968
- ChEMBL
- CHEMBL1855
- Action
- Agonist (ChEMBL)
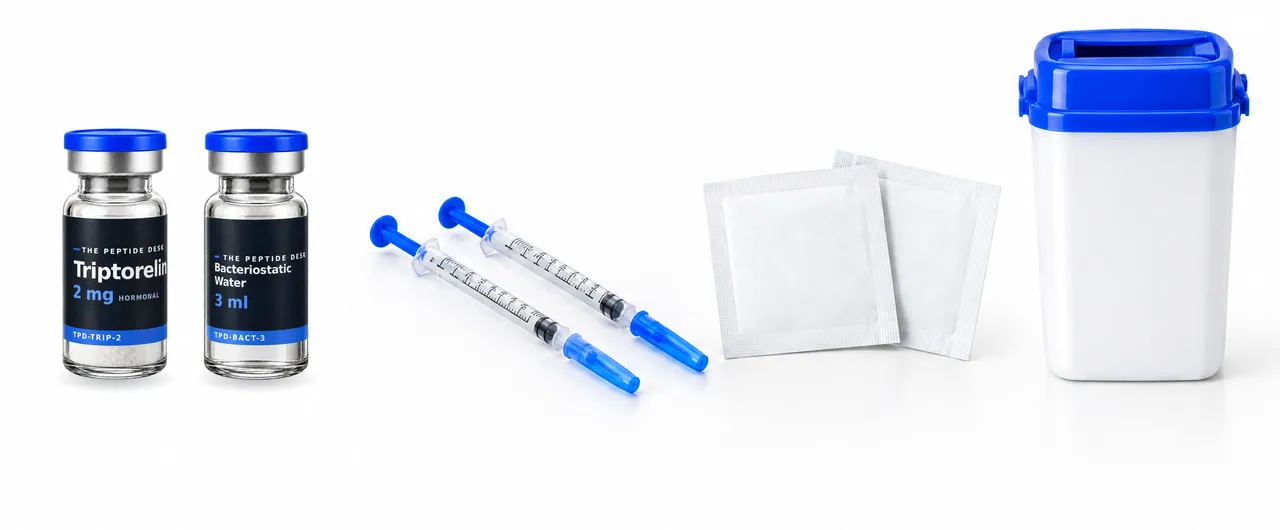
What you need
Before you start, have everything ready:
Supplies
5 things, numbered as in the picture
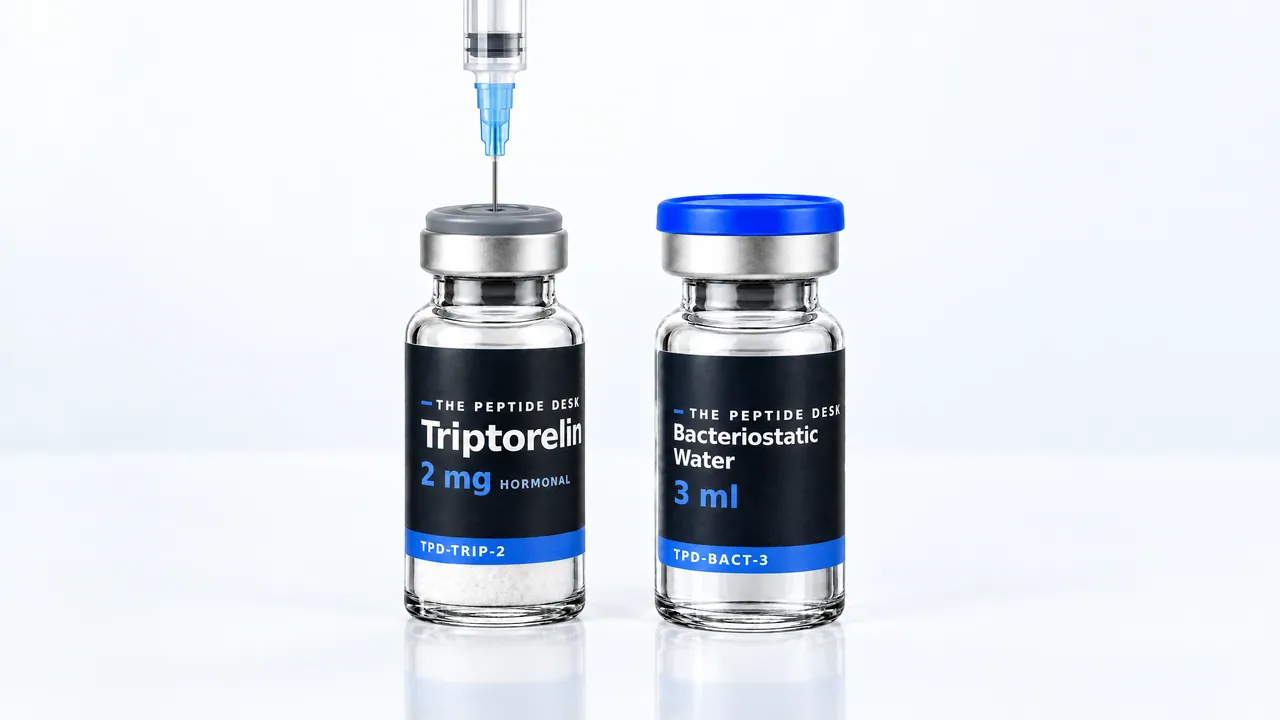
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-
Triptorelin vial
The triptorelin vial with the lyophilized powder
-
Bacteriostatic water
Bacteriostatic water to reconstitute it
-
U-100 insulin syringes
U-100 insulin syringes for use
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin site
-
Sharps container
A sealable container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
A note on dose magnitude: triptorelin is a highly potent peptide, with relevant amounts in the tenths-of-a-milligram range. That makes clean reconstitution and accurate reading on the insulin syringe especially important.
Reconstitution
The powder is dissolved with bacteriostatic water. How much water you use determines the concentration and therefore how many units you later draw on the insulin syringe for your dose. Because triptorelin is often worked with in very small amounts, more solvent tends to make sense so the unit count you have to read off does not become tiny.
You can use the peptide calculator for exactly this: pick the vial size and water amount to see the concentration and the units per dose right away.
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
In research discussion, triptorelin is usually injected subcutaneously into the fatty tissue under the skin (the approved depot products, by contrast, are intramuscular - a different, long-acting format). Typical subcutaneous sites are the abdomen (avoiding the area right around the navel), the front and the inner side of the thigh, or the back of the upper arm.
Injection
Where and at what angle
Pick a spot or switch the angle. Subcutaneous means: into the fat layer, not the muscle.
Rotate the spot each time, never the same one twice in a row.
Rule of thumb: where there is more fat under the skin, insert straight at 90 degrees. In lean people with little fat, 45 degrees, so the needle stays in the fat layer. Simplified diagram.
-
Clean the skin site with an alcohol swab and let it dry
-
Pinch up a small fold of skin
-
Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
-
Inject slowly, wait briefly, withdraw the needle
-
Put the needle straight into the sharps container
Rotate the injection site every time.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
The evidence base for triptorelin is extensive because it is an established drug:
- Prostate cancer: In a randomized trial, the triptorelin depot lowered and held testosterone at castration levels just as reliably as the comparator leuprolide, with a slightly slower onset (BJU International, 2003).
- Deep suppression: A pooled analysis of 920 patients showed that the depot formats pushed testosterone below even very low thresholds in the large majority (Advances in Therapy, 2016).
- Acute push: In delayed puberty, a single dose of triptorelin was used as a stimulation test - here the acute LH/FSH/testosterone rise is clearly measurable, the flare counterpart to chronic suppression (Turkish Journal of Pediatrics, 2001).
- Endometriosis: A review summarizes mechanism, pharmacokinetics and clinical data and describes how the hormone reduction triggered by continuous dosing was studied in the research context (Expert Opinion on Pharmacotherapy, 2014).
Important: all of this data comes from clearly defined medical indications under controlled conditions. Transferring it to other usage ideas is not backed by corresponding studies.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Testosterone at castration level1
Share of men in percent, 284 men, monthly depot over 9 months
Triptorelin lowered testosterone a little more slowly but then kept it down just as reliably. The trial found no harm from the slower onset.
Testosterone below 20 ng/dl2
Share in percent, pooled analysis of 9 trials with 920 men
Triptorelin: Month 1 +79.0%, Month 3 +92.0%, Month 6 +93.0%, Month 9 +90.0%, Month 12 +91.0%.
The usual threshold for castration level is 50 ng/dl. The analysis tested the stricter threshold of 20 ng/dl and is retrospective.
Testosterone 24 hours after a single dose3
Mean values in ng/dl, 23 boys aged 14 to 16.5 without signs of puberty
LH after 4 hours also clearly separated the groups, at 33.2 versus 3.3 mIU/ml. The short rise is the counterpart to the shutdown with continuous dosing.
Research status
Where the research stands
A selection of registered trials testing triptorelin. Often they concern new depot forms or triptorelin as a partner of other treatments. As of 26 Oct 2026. 6
- Preclinical Pituitary cells: stronger LH release than GnRH
- Phase 1 no registered trial
- Phase 2 2 trials, 1 completed, 1 stopped early
- Phase 3 7 trials, 6 completed
- Approval in the US since 2000 as a depot
Show all 11 phase 2, 3 and 4 trials on a timelineHide timeline
NCT00124514 · 31 participants, started Jun 2003, primary endpoint reached Mar 2014.
Registry entry ↗ · Results not yet in PubMed
NCT00090844 · 49 participants, started Jul 2004, stopped early May 2008.
TEXT · NCT00066703 · 2,672 participants, started Nov 2003, primary endpoint reached Mar 2011. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
NCT00667069 · 424 participants, started Apr 2008, primary endpoint reached Apr 2020. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
DECAPUB · NCT00909844 · 35 participants, started Apr 2008, primary endpoint reached Apr 2015.
Registry entry ↗ · Results not yet in PubMed
NCT03232281 · 300 participants, started Jul 2017, primary endpoint reached May 2019.
Registry entry ↗ · Results not yet in PubMed
NCT05029622 · 66 participants, started Aug 2021, primary endpoint reached Aug 2022.
Registry entry ↗ · Results not yet in PubMed
TriptoSwitch · NCT05458856 · 147 participants, started Aug 2022, primary endpoint reached Jul 2024.
Registry entry ↗ · Results not yet in PubMed
ProFertil · NCT05328258 · 500 participants (planned), started Mar 2023, primary endpoint planned Jan 2028.
NCT01161563 · 118 participants, started Jul 2010, primary endpoint reached Apr 2011. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
PRIORITI · NCT01753297 · 226 participants, started Dec 2012, primary endpoint reached Sept 2019.
Registry entry ↗ · Results not yet in PubMed
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026, grey = stopped early.
Side effects
Because triptorelin intervenes directly in the hormone axis, the reported effects are mainly hormonal. Known from clinical data and the label:
- Flare phase: The initial testosterone/estradiol rise can temporarily amplify hormone-dependent symptoms. In prostate cancer use, that is precisely a documented risk (tumor flare).
- Suppression effects: With continuous dosing, the typical consequences of lowered sex hormone levels appear - reported among others are hot flashes, libido changes as well as mood and energy swings.
- Metabolic: The label notes possible metabolic changes with longer GnRH agonist use (e.g. blood sugar, blood lipids).
- Local: Injection site reactions, as with any injection.
Intervening in the hormone axis is not a trivial band-aid topic. Anyone experimenting here should be aware of how deep the intervention runs.
Tolerability
Side effects on the monthly depot
Out of 100 men with prostate cancer on the monthly depot, how many had the event (US prescribing information).
| Event | Triptorelin |
|---|---|
| Hot flushes5 | 59% |
| Skeletal pain5 | 12% |
| Impotence5 | 7% |
| Headache5 | 5% |
| Hypertension5 | 4% |
| Injection site pain5 | 4% |
Most complaints follow from the lowered testosterone. The prescribing information also warns of tumour flare at the start, of changes in blood sugar and blood lipids and of cardiovascular risks.5
Storage
The undissolved powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. Once mixed, it keeps for at least 4 to 6 months in the fridge (2 to 8 °C). The bacteriostatic water brings a preservative that keeps the dissolved form stable longer. Because of the small working amounts, it is worth labeling the vial cleanly (date, concentration) so nothing gets mixed up the next time you draw.
Shelf life
How long it keeps
Robust, no fridge needed. Keeps for several months without trouble.
Keeps for at least 4 to 6 months. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial






