What is ACTH 1-39?
ACTH 1-39 is adrenocorticotropic hormone in its full length - 39 amino acids, cleaved from the large precursor protein POMC (proopiomelanocortin) in the pituitary. So it is not a synthetic fragment but the complete endogenous signaling molecule that drives the adrenal glands.
Clinically, ACTH exists as an approved product (Acthar Gel, repository corticotropin) - used for infantile spasms and acute MS flares. Diagnostically, the HPA axis is usually tested with short synthetic analogs instead (ACTH 1-24 / cosyntropin), not the full-length peptide. That is an important distinction to keep in mind.
Here ACTH 1-39 is framed strictly as a research substance. This information serves research and educational purposes only. No medical recommendations.
Comparison
Melanocortins in the lexicon
ACTH belongs to the melanocortin family. Which entries address which melanocortin receptors, as stated in the TPD lexicon. Tap a card to open its entry.
Simplified: only ACTH addresses MC2R and so controls the adrenal gland. The melanotans act on pigment and appetite, KPV without receptor action. 95
How it works
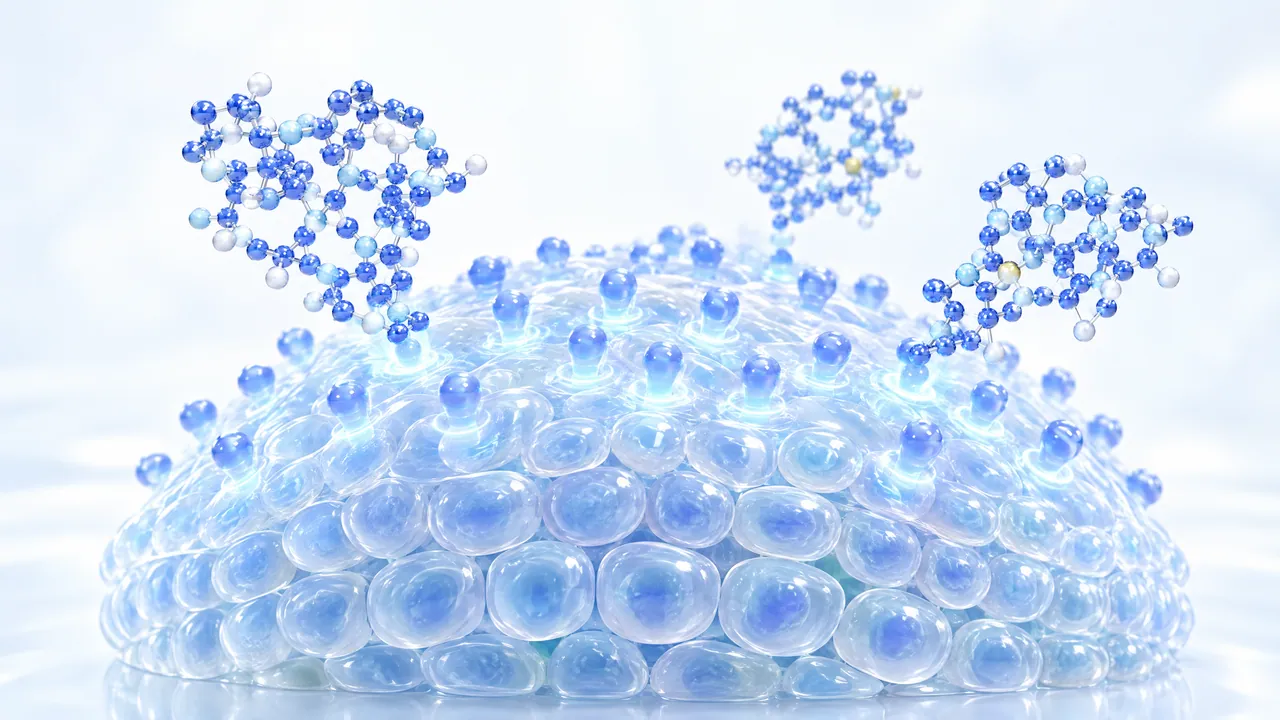
ACTH binds the melanocortin-2 receptor (MC2R) on the cells of the adrenal cortex. MC2R is the only melanocortin receptor that responds exclusively to ACTH - and it needs an additional small accessory protein (MRAP) to function at all.
Binding activates adenylyl cyclase via the Gs protein, cAMP rises, protein kinase A fires up. This drives cortisol synthesis in the zona fasciculata - that is the main pathway. Acutely, ACTH can also nudge aldosterone production in the zona glomerulosa, though aldosterone is primarily governed by angiotensin and potassium.
Through its first amino acids, ACTH shares kinship with the melanocyte-stimulating hormones (MSH) and can also engage MC1R - hence the known pigment component. In the body the whole thing runs as a pulsatile, time-of-day-dependent signal with a short half-life of roughly 10 to 20 minutes.
Where it acts
Where ACTH acts
Tap a point or a card. Colour = receptor, grey = observed.
- Adrenal gland (on the kidney)
MC2R activated, cortisol and briefly aldosterone rise1
MC2R - Pituitary gland
Releases ACTH in pulses with a daily rhythm, high cortisol brakes release2
Observed in trials - Circulation
Rise in blood pressure, salt and water retention, potassium falls6
Observed in trials - Skin
According to the label also binds melanocortin receptors, acne and skin changes as side effects6
Observed in trials
Targets in the ChEMBL database9
Compound CHEMBL1201610: one recorded mechanism, agonist with direct binding to the human receptor.
- Gene
- MC2R
- UniProt
- Q01718
- ChEMBL
- CHEMBL1965
- Action
- Agonist, direct binding
What you need
Before you start, have everything ready:
Supplies
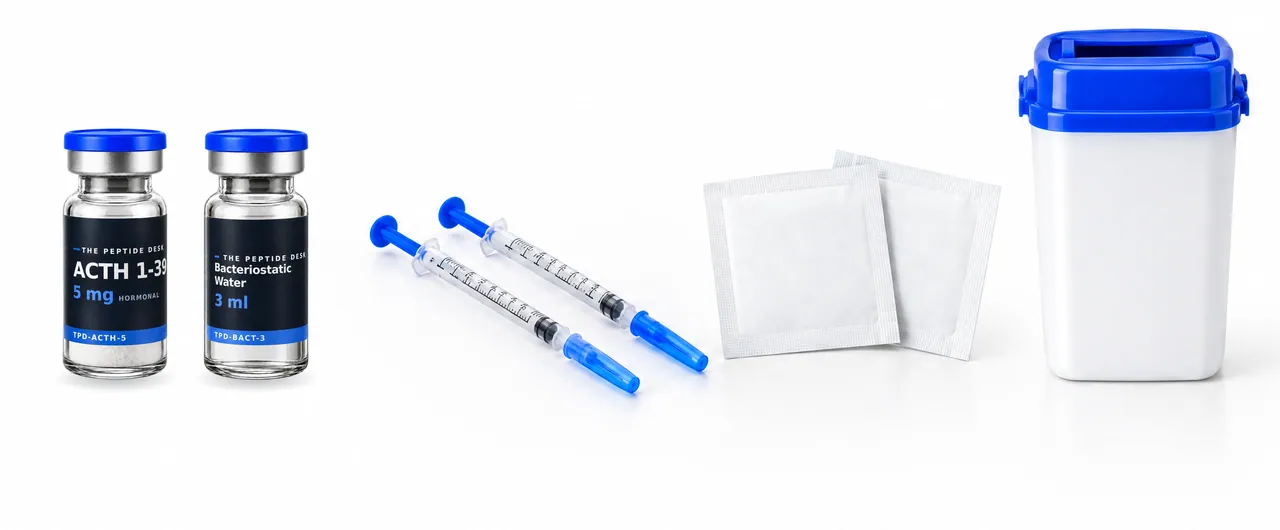
5 things, numbered as in the picture
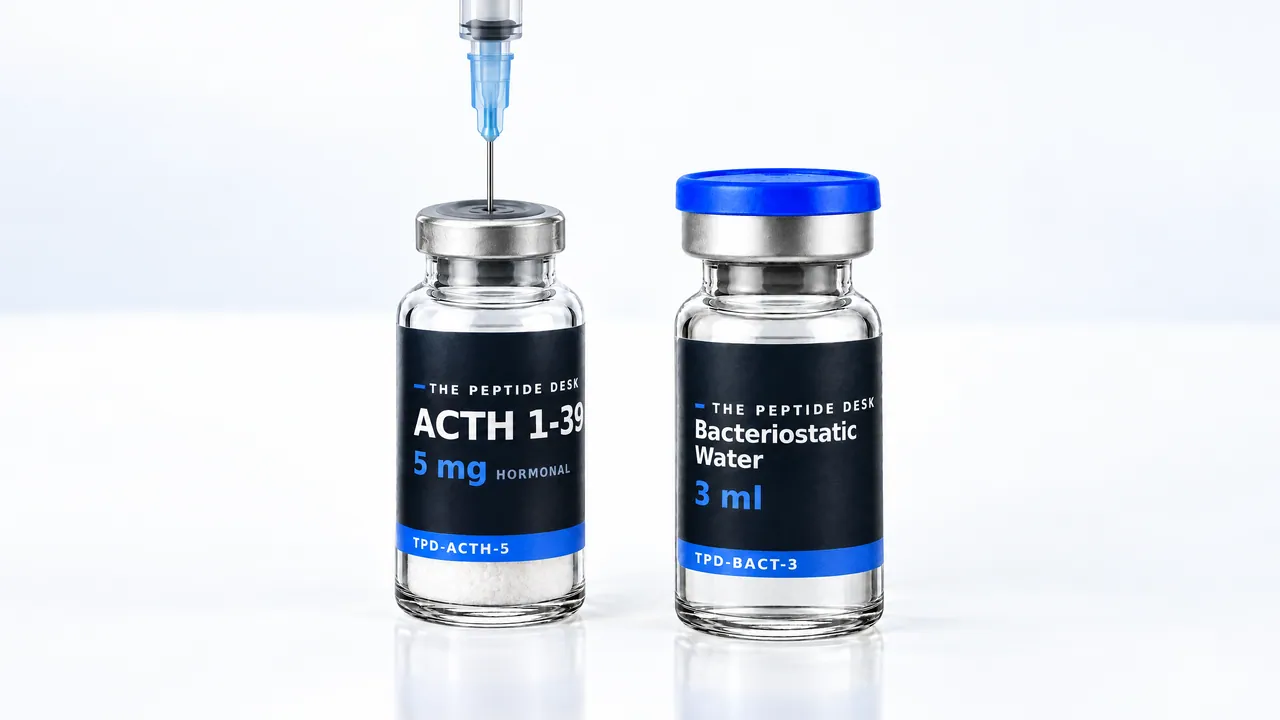
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-

ACTH 1-39 vial
The ACTH 1-39 vial with the freeze-dried powder
-
Bacteriostatic water
Bacteriostatic water for reconstitution
-
U-100 insulin syringes
U-100 insulin syringes for administration
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin site
-
Sharps container
A sealable container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
Reconstitution
The powder is dissolved with bacteriostatic water. How much water you use determines the concentration and therefore how many units you draw on the insulin syringe.
Use the peptide calculator for exactly this: pick vial size and water volume. For ACTH 1-39 it deliberately shows no dose steps, only the concentration, because there is no protocol for repeated use. Example: a 5mg vial with 2ml water gives 2.5mg per ml, 0.25mg is then 10 units, 0.05mg 2 units on the U-100 syringe. Aqueous ACTH acts fast and short, which sets it apart from depot preparations.
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
The injection is subcutaneous, into the fat layer under the skin. Common spots are the abdomen (keep about two finger-widths clear of the navel), the front and the inner side of the thigh, or the back of the upper arm.
The short version:
Injection
Where and at what angle
Pick a spot or switch the angle. Subcutaneous means: into the fat layer, not the muscle.
Rotate the spot each time, never the same one twice in a row.
Rule of thumb: where there is more fat under the skin, insert straight at 90 degrees. In lean people with little fat, 45 degrees, so the needle stays in the fat layer. Simplified diagram.
-
Clean the spot with an alcohol swab and let it dry
-
Pinch up a small fold of skin
-
Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
-
Inject slowly, wait a moment, then withdraw
-
Put the needle straight into the sharps container
ACTH 1-39 is only classed as a single dose here (see Dosing), so rotating sites does not apply.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
The physiology of ACTH has been well described for decades. Reviews of the HPA axis show that ACTH and cortisol are released in pulsatile, time-of-day-dependent waves and that this rhythm pattern matters more for the effect than a constant level (Lightman et al. 2020).
At the receptor level, MC2R as the ACTH-specific switch and its dependence on the accessory protein MRAP are well documented (Endotext, ACTH Action on the Adrenals). Diagnostically, the ACTH stimulation test with cosyntropin is established, including its known pitfalls around interpretation and thresholds (Burgos et al. 2019). For the full-length peptide itself there is a dose-response study in healthy men: subcutaneously, even 5mcg of synthetic ACTH 1-39 raised cortisol and aldosterone clearly. The curve is very steep at first (Oelkers et al. 1988).
What is missing: controlled data on ACTH 1-39 as a repeatedly subcutaneously applied research substance outside the approved indications. Endocrinology knows the hormone, but what is practiced in the research scene is not what was studied. Stay sober here.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
How strongly cortisol rises with little ACTH1
Share of the maximum cortisol rise within the first hour, nine healthy men
Almost 80 percent according to the abstract. Synthetic human ACTH 1-39 in increasing amounts under the skin, the highest study dose was 30 mcg. Even small amounts clearly raised cortisol, aldosterone and 18-hydroxycorticosterone, the curve is very steep at first.
Research status
Where the research stands
Corticotropin has been approved since 1950. On ClinicalTrials.gov 223 trials name corticotropin, many of them only use it as a test of the adrenal gland. Shown are trials that test ACTH as a treatment, including a phase 3 trial with synthetic ACTH 1-39 as a gel. As of 26 Oct 2026. 8
- Preclinical Principle: activation of MC2R in the adrenal cortex
- Phase 1 no registered trial
- Phase 2 no registered trial
- Phase 3 6 trials, 3 completed, 1 stopped early
- Approval as corticotropin since 1950
Show all 6 phase 3 trials on a timelineHide timeline
NCT02290444 · 64 participants, started Aug 2013, primary endpoint reached Nov 2018.
Registry entry ↗ · Results not yet in PubMed
NCT02132195 · 31 participants, started May 2014, primary endpoint reached Jan 2018.
Registry entry ↗ · Results not yet in PubMed
NCT02282930 · 20 participants, started Mar 2015, primary endpoint reached Jun 2018.
Registry entry ↗ · Results not yet in PubMed
NCT03068754 · 143 participants, started Jun 2017, stopped early Nov 2019.
NCT05696613 · 148 participants (planned), started Mar 2023, primary endpoint planned Apr 2027.
NCT06079788 · 140 participants (planned), started Nov 2023, primary endpoint planned Jun 2026.
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026, grey = stopped early.
Side effects
ACTH does not act directly but ramps up the body's own cortisol production - so its side effects are essentially those of elevated glucocorticoid levels. Known from the Acthar data: fluid and sodium retention, rising blood pressure, mood and sleep changes, elevated blood sugar, increased appetite.
Prolonged or high use can affect the HPA axis and dampen the immune system. Through the MSH kinship (MC1R), pigment changes are conceivable. At the injection site, the usual local reactions.
Anyone with high blood pressure, a tendency toward diabetes, or a known adrenal issue should view ACTH especially critically. When in doubt: stay low or skip it.
Tolerability
Side effects of the depot product
The only table with frequencies in the label comes from infants on a depot product. It shows how cortisol-typical side effects increase with the amount. There was no placebo group.
| Event | Depot, recommended regimen | Depot, higher regimen |
|---|---|---|
| Infections6 | 20% | 46% |
| Cushingoid appearance6 | 3% | 22% |
| High blood pressure6 | 11% | 19% |
| Irritability6 | 7% | 19% |
| Acne6 | 0% | 14% |
For adults the label lists after approval among others fluid retention, insomnia, headache and raised blood glucose. Longer use can suppress the body's own hormone axis, after stopping adrenal insufficiency may follow.6
Storage
Store the undissolved powder cool and dark. Once mixed, it keeps for at least 4 to 6 months in the fridge (2 to 8 °C).
Shelf life
How long it keeps
Keep the undissolved powder cool and away from light.
Keeps for at least 4 to 6 months.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial