What is Test/Tren Long 300?
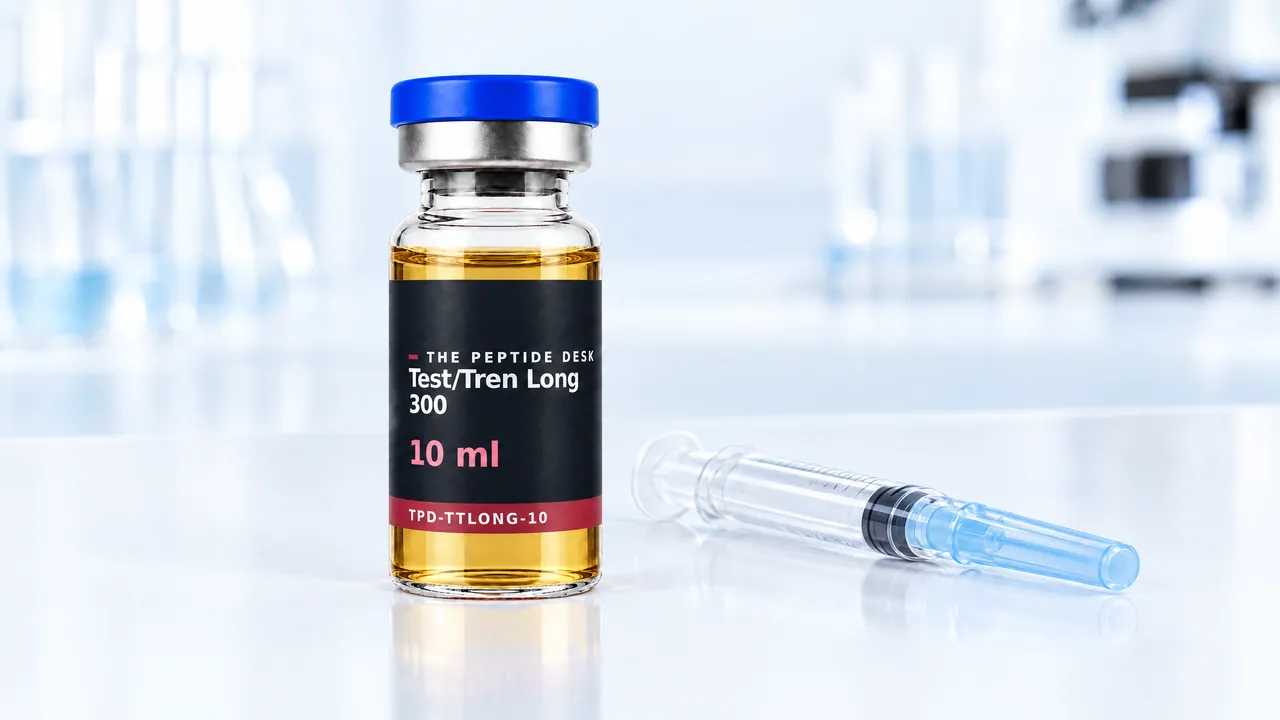
Test/Tren Long 300 is a ready-made oil solution with 200mg testosterone enanthate and 100mg trenbolone enanthate per ml, 300mg/ml in total. One vial holds 10 ml and needs no mixing. "Long" refers to the long enanthate esters of both compounds.
The 2:1 ratio means there is always twice as much testosterone as trenbolone in play, so the testosterone base is built in. Trenbolone comes from livestock use and was never approved for humans. Because of its side-effect profile the blend is nothing for beginners.
This information is for research and educational purposes only. No medical advice.
Comparison
Testosterone and trenbolone in four oils
Which compounds each oil contains, as stated in the TPD lexicon. Tap a card to open its entry.
Simplified: the same compounds do not mean the same amount per ml. Every extra compound brings its own side effects.
How it works
Both compounds bind the androgen receptor in muscle and drive protein synthesis and strength. Trenbolone binds much more strongly than testosterone, does not aromatize to estradiol and holds little water. It also acts on the progesterone receptor, though, which can favor prolactin effects.
Testosterone keeps estradiol and DHT in a normal range, which supports libido and wellbeing. Both enanthate esters have a half-life of several days, so levels stay stable with two doses per week. On the flip side, side effects take one to two weeks to fade after stopping.
Where it acts
One receptor, several organs
Tap a point or a card. Grey = effect seen in trials.
- Hypothalamus and pituitary
LH and FSH suppressed as long as testosterone was raised6
Observed in trials - Testes
Sperm production suppressed: no sperm in 65 percent after 6 months, recovery within months after stopping7
Observed in trials - Blood
Haemoglobin and haematocrit rose with the testosterone dose, more in older men8
Observed in trials - Heart
Pumping function lower in long-term users (52 vs 63 percent), more coronary plaque5
Observed in trials - Skeletal muscle
More muscle and bone mass under trenbolone in various animal species2
Observed in trials - Fat tissue
Fat mass fell as testosterone levels rose1
Observed in trials - Skin
Acne in 28 of 100 users, breast tissue growth in 199
Observed in trials
Targets in the ChEMBL database11
Compound CHEMBL1200335: one recorded mechanism, agonist with direct binding to the human receptor.
- Gene
- AR
- UniProt
- P10275
- ChEMBL
- CHEMBL1871
- Action
- Agonist, direct binding
Use and dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
Injection
Intramuscular into the glute, thigh or shoulder, with a thick needle to draw up and a thin one (23G to 25G) to inject. Disinfect the stopper and the site first and rotate sites regularly. Aspirating first and injecting slowly lowers the risk of tren cough, a brief coughing fit right after the injection.
Both esters are long, but trenbolone irritates subcutaneous tissue more. Subcutaneous use therefore only at very small volumes and only if well tolerated.
What the research shows
For testosterone a dose-response study shows that fat-free mass and strength rise with the dose while HDL falls in step (Bhasin, 2001). Trenbolone is described as a very potent anabolic with reduced androgenic and estrogenic activity; the evidence comes almost entirely from animal studies (Yarrow, 2010). There is no study of the fixed combination.
Reviews and observational studies of steroid users show shifted lipids (Achar, 2010), lastingly higher blood pressure with a stiffer aorta (Rasmussen, 2018) plus, with long-term use, weaker heart pumping function and more coronary plaque (Baggish, 2017).
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Fat-free mass after 20 weeks1
Gain in kg in the three higher of five dose levels of testosterone enanthate, the body's own production was switched off with medication
The two lowest levels are not shown here. Strength, haemoglobin and IGF-1 rose with the testosterone level while fat mass and HDL cholesterol fell. Trial with testosterone alone.
High blood pressure in users4
Share with systolic hypertension on 24-hour monitoring, strength athletes
Systolic 24-hour average 132 vs 124 mmHg. Aortic distensibility was 21 percent lower in current and in former users than in controls, so the aorta was stiffer.
Pumping function of the heart5
Left ventricular ejection fraction in percent, experienced strength athletes aged 34 to 54
Cross-sectional study, users with at least 2 years of total use. Coronary plaque had a median of 3 vs 0, the longer the total use, the more plaque.

Research status
Where the research stands
There is no study on the blend and the registry finds none on trenbolone. Shown are registered trials with testosterone enanthate given by injection. As of 26 Oct 2026. 10
- Preclinical Trenbolone: more muscle and bone mass, less fat in various animal species
- Phase 1 9 trials on components, 8 completed, 1 stopped early
- Phase 2 13 trials on components, 8 completed, 1 stopped early
- Phase 3 7 trials on components, 6 completed
- Approval not yet
Show all 23 phase 2, 3 and 4 trials on a timelineHide timeline
NCT00260143 · 61 participants, started May 2003, primary endpoint reached Jun 2006.
Registry entry ↗ · Results not yet in PubMed
NCT00475501 · 60 participants, started Jan 2007, primary endpoint reached Mar 2012. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
NCT01887418 · 39 participants, started Sept 2013, primary endpoint reached Jan 2014.
Registry entry ↗ · Results not yet in PubMed
RESTORE · NCT02090114 · 112 participants, started Aug 2014, primary endpoint reached Nov 2021. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
TRANSFORMER · NCT02286921 · 222 participants, started Jan 2015, primary endpoint reached Oct 2018. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
NCT02229617 · 14 participants, started Jul 2015, primary endpoint reached May 2016.
Registry entry ↗ · Results not yet in PubMed
NCT02777242 · 66 participants, started Jun 2016, primary endpoint reached Aug 2016.
Registry entry ↗ · Results not yet in PubMed
NCT02248701 · 33 participants, started Apr 2017, stopped early Aug 2021. Tests several agents.
HiTeCH · NCT03522064 · 30 participants (planned), started Jul 2018, primary endpoint planned Sept 2026. Tests several agents.
NCT03516812 · 36 participants, started Aug 2018, primary endpoint reached Mar 2021. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
NCT04363164 · 150 participants (planned), started Aug 2020, primary endpoint planned Jul 2027. Tests several agents.
NCT04460872 · 21 participants (planned), started Jan 2021, primary endpoint planned Jan 2026.
WOMBAT · NCT06594926 · 69 participants (planned), started Aug 2024, primary endpoint planned Dec 2026.
NCT00161304 · 44 participants, started Apr 2003, primary endpoint reached Aug 2004.
Registry entry ↗ · Results not yet in PubMed
NCT00965341 · 53 participants, started Sept 2009, primary endpoint reached Sept 2012.
Registry entry ↗ · Results not yet in PubMed
OPTIMen · NCT01275365 · 92 participants, started May 2011, primary endpoint reached Jan 2017.
Registry entry ↗ · Results not yet in PubMed
NCT01595581 · 14 participants, started Apr 2012, primary endpoint reached May 2015.
Registry entry ↗ · Results not yet in PubMed
STEADY · NCT02159469 · 150 participants, started Jul 2014, primary endpoint reached Feb 2015.
Registry entry ↗ · Results not yet in PubMed
NCT02504541 · 133 participants, started Jul 2015, primary endpoint reached Jun 2016.
Registry entry ↗ · Results not yet in PubMed
NCT06689085 · 100 participants (planned), started Mar 2025, primary endpoint planned Mar 2028.
NCT00493987 · 184 participants (planned), started Nov 2002, primary endpoint reached Dec 2009. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
NCT00957801 · 29 participants, started Mar 2009, primary endpoint reached Dec 2015. Tests several agents.
Registry entry ↗ · Results not yet in PubMed
OPS · NCT02734238 · 53 participants, started Apr 2016, primary endpoint reached Dec 2017.
Registry entry ↗ · Results not yet in PubMed
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026, grey = stopped early. Phase 1: 9 trials on safety and pharmacokinetics, not shown as bars.
Side effects
- Prolactin: trenbolone can cause prolactin effects, with libido and erection problems. Add prolactin to the bloodwork.
- Lipids: HDL drops sharply and LDL rises. Trenbolone is considered especially unfavorable here.
- Blood pressure and heart: blood pressure and resting heart rate go up, endurance and breathing under load suffer. Measure regularly.
- Sleep: trouble falling asleep, restless sleep and night sweats are typical.
- Mood: irritability, restlessness and aggression are reported often.
- Estrogen and blood count: the testosterone share aromatizes, hematocrit rises.
- Hormone axis: your own production is strongly suppressed, acne and hair loss if predisposed are common.
Blood pressure, lipids, prolactin and hematocrit should be checked before, during and after a cycle.
Tolerability
Frequency in the HAARLEM study
Out of 100 users, how many had the event. One cohort without a comparison group, participants chose compounds and amounts themselves.
| Event | All 100 users |
|---|---|
| At least one side effect9 | 100% |
| Lower libido after the cycle9 | 58% |
| Fluid retention during the cycle9 | 56% |
| Agitation during the cycle9 | 36% |
| Acne9 | 28% |
| Breast tissue growth (gynecomastia)9 | 19% |
Four participants had a serious event: heart failure, pancreatitis, suicidal thoughts and a flare of ulcerative colitis. One year after the start the observed effects were back at baseline. Effects typical of trenbolone such as sleep problems were not reported separately.9
Storage
Store at room temperature, in the dark and in the original packaging, out of reach of children. Do not put it in the fridge, because cold makes the compounds crystallize out of the oil. If you see crystals, warm the vial in your hand or in warm water and swirl until the solution is clear again. Disinfect the stopper before every draw.