This information is for research and educational purposes only. No medical recommendations. Products are not approved for human use. For health questions, consult a doctor.

Lexicon

Amlodipine (Norvasc)

The calcium channel blocker that leaves your heart rate alone - which makes it the most training-friendly option.

3 min read 8 sources

Large blue 3D molecule model with light blue, white and one green atom above a white podium with a glowing rim in a bright lab
Approved · in the USA since 1992

Summary

At a glance

Sources checked on 26 Oct 2026

Half-life
30 to 50 hours

steady level only after 7 to 8 days of daily dosing5

Largest head-to-head trial
33,357 participants

ALLHAT: primary endpoint after 6 years the same as with the diuretic chlorthalidone1

Heart failure in ALLHAT
+38 %

relative risk versus chlorthalidone, 10.2 versus 7.7 percent after 6 years1

Strokes in ASCOT
-23 %

amlodipine-based regimen versus atenolol-based, hazard ratio 0.772

Ankle swelling (oedema)
10.8 %

at the highest study dose, 0.6 percent with placebo5

  • Amlodipine is a dihydropyridine calcium channel blocker. It blocks voltage-gated L-type calcium channels in the vessel wall, the arteries widen and blood pressure falls.75
  • The half-life of 30 to 50 hours explains why one dose a day is enough and why the full effect only builds after about a week.5
  • In ALLHAT with more than 33,000 high-risk patients amlodipine matched a diuretic on the primary endpoint, but heart failure occurred 38 percent more often.1
  • In ASCOT an amlodipine-based regimen did better than an atenolol-based one: fewer strokes, fewer deaths, less new diabetes. In VALUE blood pressure fell faster than with valsartan.23
  • The most common side effect is swollen ankles, clearly dose-dependent. Amlodipine has been approved in the USA since 1992. Everything here is research, not a recommendation.56
Profile

Updated July 2026

How long does it stay in the body?

Share left after one dose, calculated with a half-life of ~1.7 days

Half-life ~1.7 days
After 3.3 days: 25 %
Day 1, next dose · 66 %Day 1.7 · 49 %Day 3.3 · 25 %Day 5 · 12.5 %Day 8.3 · 3.2 %

Simplified model without an absorption phase, half-life from the TPD lexicon. The lexicon gives 1.3 to 2.1 days, we calculate with the middle.

Class
Calcium channel blocker

dihydropyridine type

Use
Oral

once daily

Half-life
30 to 50 hours
Onset
7 to 10 days to full effect
Status
Clinically approved

in wide use since the 1990s

Contents 12 sections
  1. At a glance
  2. What is amlodipine?
  3. How it works
  4. Use and dosing
  5. What the research shows
  6. Research status
  7. Side effects
  8. Storage
  9. Related compounds
  10. FAQ
  11. Glossary
  12. Sources

What is amlodipine?

Amlodipine is a calcium channel blocker of the dihydropyridine type. It blocks calcium entry into the smooth muscle of the arterial wall. Without calcium the muscle cannot contract, the vessels widen, peripheral resistance falls and blood pressure with it.

The point that makes it interesting in a training context: amlodipine acts almost exclusively on the vessels and barely on the heart itself. It does not lower heart rate. A beta blocker caps your maximum heart rate and with it, measurably, your endurance performance. A calcium channel blocker does not.

This information is for research and educational purposes only. No medical advice.

Comparison

Blood pressure drugs compared

Blood pressure drugs from the TPD lexicon, as described there. Tap a card to open its entry.

Simplified: each class acts at a different point. Amlodipine widens the arteries and does not lower heart rate, beta blockers slow the heart. 71

How it works

The half-life of 30 to 50 hours is unusually long for a blood pressure agent and explains three things at once. First, one dose per day is enough. Second, it takes seven to ten days for the full effect to appear, because the level has to build. Third, it keeps working for days after stopping.

In practice: anyone measuring after three days and finding the target range unmet measured too early. Increasing at that point regularly drives pressure unnecessarily low once the build-up finishes. Conversely, a missed dose does not need catching up, the buffer is too large for that.

Where it acts

Where amlodipine acted in studies

Tap a point or a card. Colour = L-type calcium channel, grey = observed in studies.

  1. Arteries

    Less calcium entry into the vessel muscle, the arteries widen and blood pressure falls7

    CaV1.2
  2. Heart

    More heart failure than with chlorthalidone, yet not harmful in severe heart failure1

    Observed in trials
  3. Brain

    Fewer strokes than with the atenolol regimen2

    Observed in trials
  4. Glucose metabolism

    New diabetes less often than with the atenolol regimen2

    Observed in trials
  5. Liver

    About 90 percent is broken down in the liver, 40 to 60 percent higher levels in liver impairment5

    Observed in trials

Targets in the ChEMBL database7

Compound CHEMBL1491 (Amlodipin): one recorded mechanism, Blocker, direct binding.

Voltage-gated L-type calcium channel
Gene
CACNA1C
UniProt
Q13936, Q13698, Q01668, O60840
ChEMBL
CHEMBL2095229
Action
Blocker, direct binding
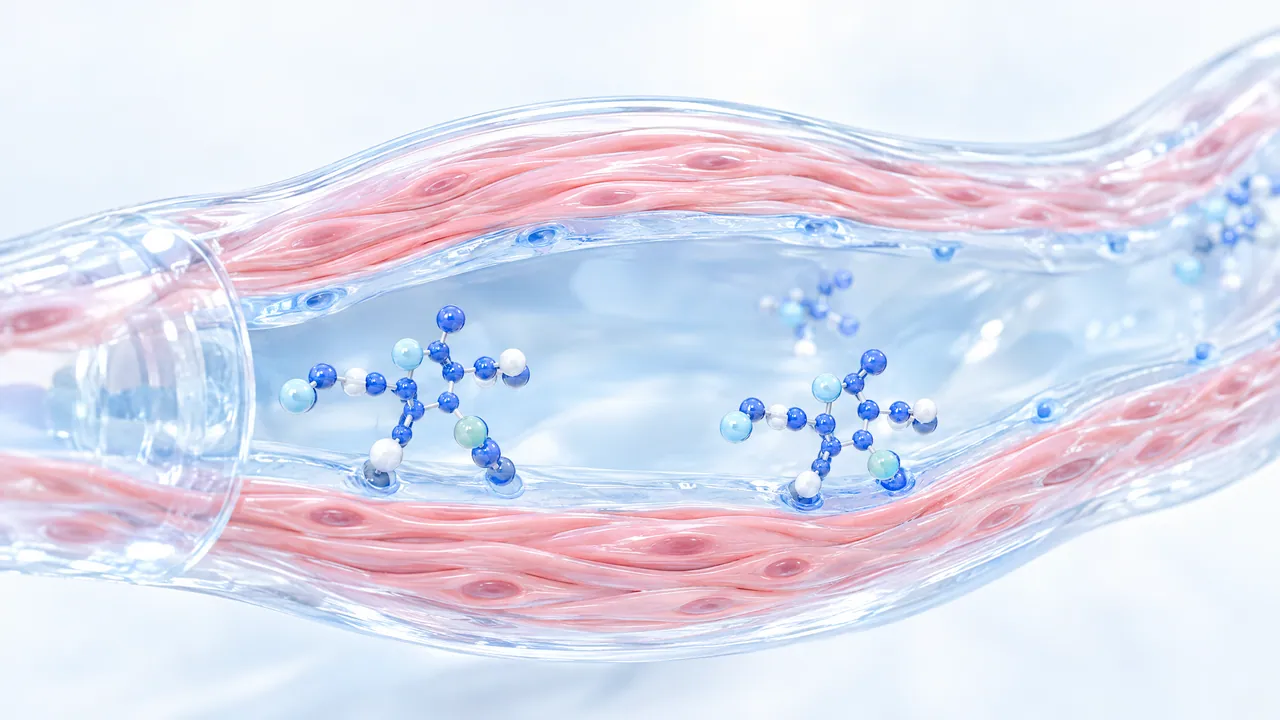
Cut-open glass artery with a pink muscle layer in its wall, blue 3D molecules floating against the vessel wall inside
Calcium channels in the vessel muscle, the artery widens. Symbolic image.

Use and dosing

Dosing

Dosing, titration and syringe

Loading the dosing information …

  • Getting started and stepping up, drawn as a staircase
  • Units on the U-100 syringe for every step
  • How long one vial lasts
White folding box with the TPD logo next to a blister with ten white tablets and two loose tablets on a bright lab bench
Tablet in a blister, one dose a day. Symbolic image.

What the research shows

The evidence is unusually dense for a blood pressure agent, but not uniformly flattering. ALLHAT (JAMA 2002) compared over 33,000 high-risk patients and found no difference in the primary endpoint between amlodipine and the diuretic chlorthalidone. But heart failure occurred 38 percent more often under amlodipine. That is the single most important caveat about the substance and belongs, honestly, on every page about it.

ASCOT-BPLA (Lancet 2005) came out clearly in amlodipine's favour: an amlodipine-based regimen beat an atenolol-based one on strokes and all-cause mortality. VALUE (Lancet 2004) showed faster pressure reduction in the first months and fewer heart attacks under amlodipine than under valsartan.

PRAISE (NEJM 1996) is the reason amlodipine may be used at all in existing heart failure: it proved safe, while older calcium channel blockers caused harm in that setting.

Study results

What the trials measured

Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.

Amlodipine versus chlorthalidone in high-risk hypertension1

Share with an event after 6 years, in percent

Fatal coronary heart disease or non-fatal heart attack1 Primary endpoint
Chlorthalidone (diuretic) 11.5%
Amlodipine or amlodipine regimen 11.3%
Heart failure1
Chlorthalidone (diuretic) 7.7%
Amlodipine or amlodipine regimen 10.2%

Values from the abstract, mean follow-up 4.9 years. No difference in the primary endpoint or all-cause mortality, heart failure more common with amlodipine (relative risk 1.38).

Amlodipine regimen versus atenolol regimen2

Share with an event over the whole trial, in percent (calculated)

Stroke2
Atenolol regimen 4.4%
Amlodipine or amlodipine regimen 3.4%
Death from any cause2
Atenolol regimen 8.5%
Amlodipine or amlodipine regimen 7.7%
New diabetes2
Atenolol regimen 8.3%
Amlodipine or amlodipine regimen 5.9%
Cardiovascular events and procedures2
Atenolol regimen 16.7%
Amlodipine or amlodipine regimen 14.1%

Percentages calculated from the events in the abstract and the group size (9,639 versus 9,618). Perindopril could be added to amlodipine, bendroflumethiazide to atenolol. The trial was stopped early.

Amlodipine regimen versus valsartan regimen3

Cardiac events and cardiac death, in percent

Primary endpoint3
Valsartan regimen 10.6%
Amlodipine or amlodipine regimen 10.4%

No difference in the primary endpoint. Blood pressure with amlodipine was 4.0/2.1 mmHg lower after one month and still 1.5/1.3 mmHg lower after one year.

Severe chronic heart failure, 6 to 33 months4

Share with an event, in percent

Death or hospital admission (primary endpoint)4
Placebo 42%
Amlodipine or amlodipine regimen 39%
Death4
Placebo 38%
Amlodipine or amlodipine regimen 33%

1,153 patients with an ejection fraction below 30 percent. Neither difference was significant: amlodipine did not make things worse, unlike older calcium channel blockers.

Glass heart model and a cut-open glass blood vessel with a pink wall on a light wooden table in front of a window overlooking water
Large outcome trials on heart and vessels. Symbolic image.

Research status

Where the research stands

Amlodipine has been approved since 1992. On ClinicalTrials.gov 728 trials list amlodipine among their interventions, often as a comparator or in combination. Shown are the two large outcome trials from this entry that are listed there. ASCOT and PRAISE ran outside the registry. As of 26 Oct 2026. 8

  1. Preclinical Development as a long-acting calcium channel blocker
  2. Phase 1 no registered trial
  3. Phase 2 no registered trial
  4. Phase 3 2 trials, 2 completed
  5. Approval in the USA since 1992
0 participants in phase 3 Approved: in the USA since 31 July 1992 (NDA 019787), ChEMBL lists amlodipine with phase 4 as the highest phase.6
Show all 2 phase 3 trials on a timelineHide timeline 2 completed 0 running 2 with results
Phase 3

Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026.

Side effects

  • Swollen ankles: by far the most common report, mostly in the evening and mostly at 10mg. Important to understand: this is not fluid retention in the sense of an excess, it is a local shift of fluid into tissue, because the small arteries widen more than the veins do. Diuretics do not help against it. Anyone affected usually does better on a lower dose plus a second agent than on 10mg alone.
  • Headache and flushing: typical in the first days, usually settles on its own.
  • Dizziness on standing: a sign that pressure sits too low.
  • Gum overgrowth: rare, but documented and relevant with long-term use.

Tolerability

Side effects by dose

From the US label: these side effects rose with the dose. The study arms are named relative to each other.

1 of 100 Placebo
2 of 100 Lowest study dose
3 of 100 Middle study dose
11 of 100 Highest study dose (10 mg)
Event PlaceboLowest study doseMiddle study doseHighest study dose (10 mg)
Oedema (swollen ankles)5 1%2%3%11%
Palpitations5 1%1%1%5%
Dizziness5 2%1%3%3%
Flushing5 0%1%1%3%

Discontinuation because of side effects about 1.5 percent versus 1 percent with placebo. Oedema was more common in women than in men (14.6 versus 5.6 percent).5

Storage

Store dry, at room temperature and protected from light. Keep out of reach of children.

Three white bottles on a bright shelf next to a folded light blue towel
Store dry, at room temperature and out of reach of children. Symbolic image.
Level · Amlodipine (Norvasc)

How the level builds up

One dose per day: each dose adds to what is left of the previous one.

Lexicon: Oral, once daily
Peak 2.94×Trough 1.94×
Day 7 · 8. dose
2.83× of the first dose
Plateau
from Day 7

96 % of the plateau after dose 8

Peak
2.94×

of the first dose

Trough
1.94×

before the next dose

Simplified model, values relative to the first dose, no dosing information. Dashed: the first dose alone, green: the plateau.

Related

Related compounds

A different path: all in the TPD lexicon.

FAQ

Common questions about Amlodipine (Norvasc)

Short answers, each backed by the sources below.

Since when has amlodipine been approved?

In the USA since 31 July 1992. ChEMBL lists amlodipine with phase 4 as the highest phase and the registry contains more than 700 trials with the drug.678

Why does it take days to reach the full effect?

The half-life is 30 to 50 hours. A steady level is only reached after 7 to 8 days of daily dosing. Food does not change absorption, 64 to 90 percent reaches the blood.5

What did ALLHAT show?

33,357 people aged 55 or older with high blood pressure and at least one other risk factor received amlodipine, lisinopril or the diuretic chlorthalidone. There was no difference in the primary endpoint (11.3 versus 11.5 percent after 6 years). Heart failure, however, was more common with amlodipine, 10.2 versus 7.7 percent.1

What did ASCOT and VALUE show?

In ASCOT with 19,257 patients the amlodipine regimen had fewer strokes (hazard ratio 0.77), fewer deaths (0.89) and less new diabetes (0.70) than the atenolol regimen. In VALUE with 15,245 patients there was no difference from valsartan in the primary endpoint, but blood pressure fell faster with amlodipine.23

Can amlodipine be used in heart failure?

In PRAISE 1,153 people with severe heart failure received amlodipine or placebo. Amlodipine did not increase illness or death, while older calcium channel blockers caused harm in this setting. The trial did not show a benefit in heart failure.4

Why do the ankles swell?

Oedema is the most common side effect and clearly dose-dependent: 0.6 percent with placebo, 1.8 percent at the lowest study dose, 10.8 percent at the highest (10 mg). Women were affected more often than men.5

Glossary

Terms explained briefly

Dotted words in the text open these explanations directly.

Calcium channel blocker
A drug that slows the entry of calcium into muscle cells. In the vessel wall the muscle relaxes as a result.
Dihydropyridine
A subgroup of calcium channel blockers that acts mainly on the vessels and hardly on the heart.
Diuretic
A water pill that makes the kidneys excrete more salt and water.
Half-life
The time until the amount in the blood has fallen by half.
Hazard ratio
The ratio of risk between two groups over time. 0.77 means about 23 percent fewer events.
Heart failure
The heart no longer pumps enough blood for the body's needs.
L-type calcium channel
A voltage-gated channel in the cell wall of heart and vessel muscle through which calcium enters.
Oedema
Swelling from fluid in the tissue, with amlodipine typically at the ankles and lower legs.
Primary endpoint
The outcome a trial is judged on, set in advance, such as heart attack or death.
Relative risk
The risk of one group divided by the risk of the comparison group. 1.38 means 38 percent more often.

Evidence

Sources

Show all 8 sourcesHide sources 4 Studies1 Trial registry3 Database checked 26 Oct 2026

Studies

  1. ALLHAT: amlodipine, lisinopril and chlorthalidone head to head

    ALLHAT Officers and Coordinators, JAMA, 2002

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  2. ASCOT-BPLA: amlodipine regimen versus atenolol regimen

    Dahlöf et al., The Lancet, 2005

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  3. VALUE: amlodipine versus valsartan at high risk

    Julius et al., The Lancet, 2004

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed
  4. PRAISE: amlodipine in severe chronic heart failure

    Packer et al., New England Journal of Medicine, 1996

    Checked 26 Oct 2026 via doi.org, Crossref, PubMed

Trial registry

  1. Trials with amlodipine on ClinicalTrials.gov

    ClinicalTrials.gov, U.S. National Library of Medicine

    Checked 26 Oct 2026 via ClinicalTrials.gov API v2

Database

  1. US prescribing information for amlodipine (side effects, pharmacokinetics)

    DailyMed, U.S. National Library of Medicine (NDA 019787, Stand 2026)

    Checked 26 Oct 2026 via openFDA Label API, DailyMed
  2. US approval of amlodipine (NDA 019787, 31 Jul 1992)

    Drugs@FDA, U.S. Food and Drug Administration

    Checked 26 Oct 2026 via openFDA-API
  3. Amlodipine in ChEMBL (mechanism and approval)

    ChEMBL, EMBL-EBI (CHEMBL1491, Mechanismus am Besilat CHEMBL1200402)

    Checked 26 Oct 2026 via ChEMBL