What is Tesamorelin?
Tesamorelin is a stabilised GHRH analogue, a synthetic version of growth-hormone-releasing hormone. It is not growth hormone (GH) itself, but nudges the pituitary to release the body's own GH in natural pulses. That is the key difference from direct GH: the body keeps control over the amount and rhythm.
Unlike the GLP-1 compounds, Tesamorelin is injected daily, usually in the evening. The half-life is very short, per the US prescribing information 26 minutes in healthy subjects and 38 minutes in HIV patients after 14 days of dosing (for newer formulations only 8 to 11 minutes after a single dose). The GH pulse it triggers and the later rise in IGF-1 act for far longer, though. It ships as a freeze-dried powder you dissolve in bacteriostatic water before the first use.
Comparison
GHRH, ghrelin or the hormone itself
Where each compound acts, as stated in the TPD lexicon. Tap a card to open its entry.
How it works
Tesamorelin binds the GHRH receptors on the pituitary and triggers a GH pulse there, similar to the one that naturally happens in deep sleep. The released GH drives IGF-1 production in the liver. A large part of the effects run through that.
In research, Tesamorelin is mainly known for one thing: it selectively reduces visceral belly fat, the fat deep in the abdomen around the organs. It does so fairly specifically, without strongly touching the subcutaneous fat. Alongside that, a positive effect on liver fat and, in one study, on cognitive performance in older subjects has been observed.
Where it acts
One receptor, several organs
Tap a point or a card. Colour = receptor, grey = effect seen in trials.
- Pituitary
Releases the body's own growth hormone in pulses11
GHRH - Liver
Liver fat fell in two studies in HIV6
Observed in trials - Belly fat
Visceral fat fell, subcutaneous fat stayed nearly the same1
Observed in trials - Blood lipids and vessels
Triglycerides fell, carotid artery wall slightly thinner7
Observed in trials - Blood sugar
HbA1c of 6.5% or more in 5 versus 1 percent on placebo11
Observed in trials
Targets in the ChEMBL database13
Compound CHEMBL1237026: one recorded mechanism, agonist with direct binding to the human receptor.
- Gene
- GHRHR
- UniProt
- Q02643
- ChEMBL
- CHEMBL2032
- Action
- Agonist, direct binding

What you need
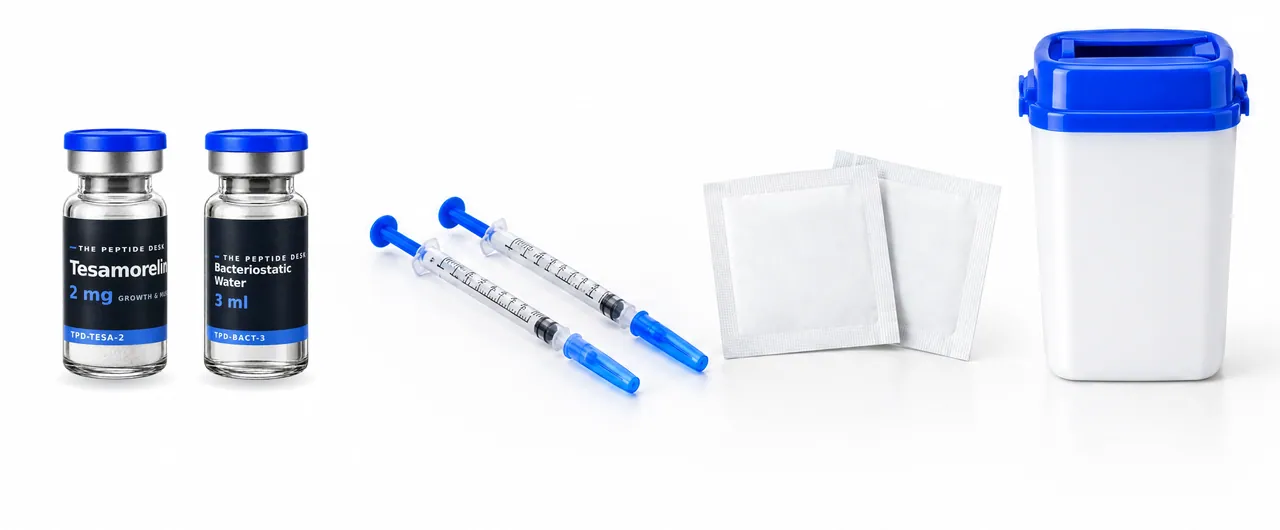
Before you start, have everything ready. Because Tesamorelin is injected daily, you need more needles accordingly:
Supplies
5 things, numbered as in the picture
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-

Tesamorelin vial
The Tesamorelin vial with the freeze-dried powder
-
Bacteriostatic water
Bacteriostatic water to dissolve it
-
U-100 insulin syringes
U-100 insulin syringes for the daily injections
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin
-
Sharps container
A sealable sharps container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
With everything clean and in one place, the rest is straightforward.
Reconstitution
The powder is dissolved in bacteriostatic water. How much water you add sets the concentration and therefore how many units you draw on the insulin syringe for your dose.
Use the peptide calculator for exactly this: pick your vial size and the water volume to instantly see the concentration and the units per dose. Roughly: less water means higher concentration and fewer units.
When dissolving, just add the bac water, it does not matter if it hits the powder directly. Then swirl or shake until everything has dissolved, both are fine.
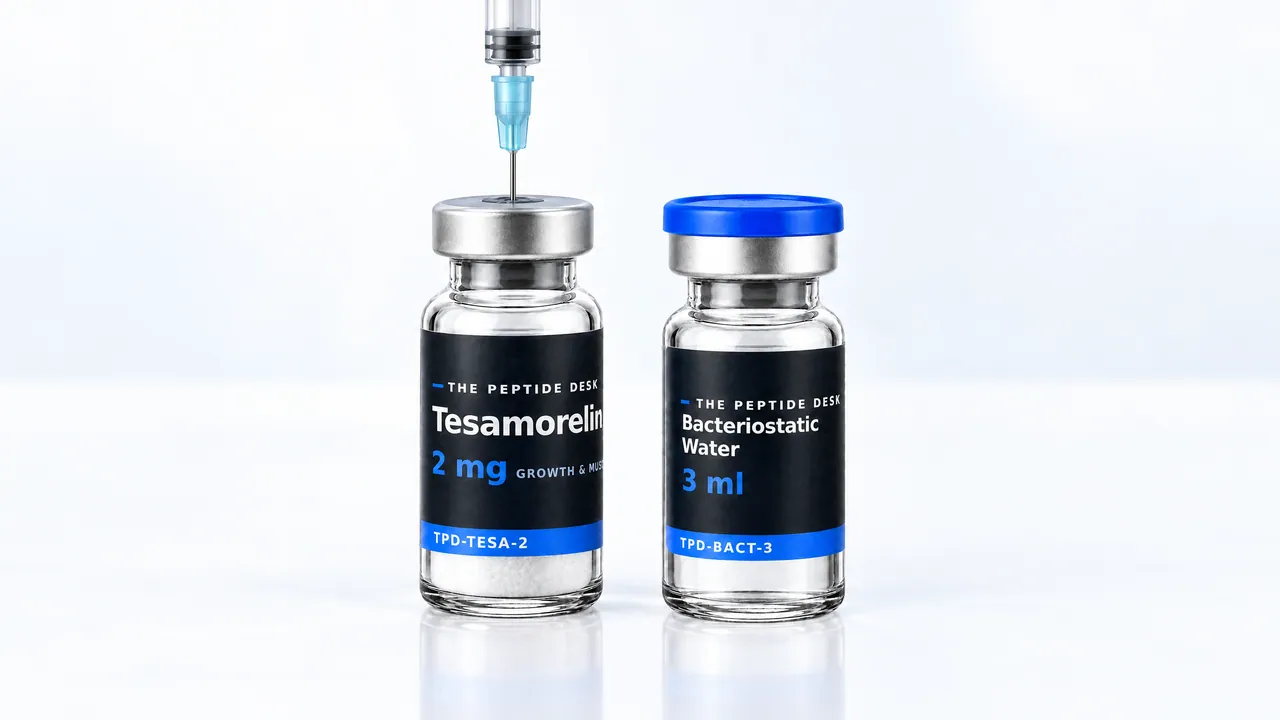
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
The injection is subcutaneous, into the fat layer under the skin, classically into the abdomen (keep about two finger-widths clear of the navel). Many inject in the evening, because the natural GH pulse comes during deep sleep anyway and the effect leans on that.
The short version:
- Clean the spot with an alcohol swab and let it dry
- Pinch up a small fold of skin
- Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
- Inject slowly, wait a moment, then withdraw
- Put the needle straight into the sharps container
Rotate the site day to day. Exactly because this is injected daily, that matters so the tissue does not get irritated.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
Tesamorelin is well studied. In the registration-grade trial (Falutz, 2007), 2mg per day over six months selectively reduced visceral belly fat while subcutaneous fat stayed largely untouched. A later trial (Stanley, 2014) confirmed this and additionally showed a drop in liver fat. In a cognition study (Baker, 2012), tesamorelin over 20 weeks had a positive effect on executive function in older subjects, while memory showed only a trend.
The individual studies with links are in the source block below.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Visceral belly fat at 26 weeks134
Mean change in percent, measured by CT in people with HIV and excess belly fat
Values as stated in the trial abstracts. Subcutaneous belly fat barely changed. Those who switched to placebo after 26 weeks quickly lost the effect again.
Liver fat at 6 months5
Median change in liver fat content (lipid to water) in percentage points, 50 participants with HIV
The net difference was 2.9 percentage points in favour of Tesamorelin. The study was small and designed as a preliminary trial.
Liver fat below 5% after 12 months6
Share of participants with normal liver fat, 61 people with HIV and fatty liver
Compared with placebo liver fat fell by 4.1 percentage points in absolute terms, 37 percent relative to baseline. Fasting glucose and HbA1c did not differ after twelve months.
IGF-1 at 26 weeks1
Mean change in blood level in percent, phase 3 trial 1
IGF-1 is made mainly in the liver when growth hormone is released. Per the US prescribing information it was clearly above the age-adjusted range in 47 percent of treated patients after 26 weeks.

Research status
Where the research stands
From lab experiments to approval in the USA: registered trials with status, participants and results. As of 25 Oct 2026. 12
- Preclinical Binding to the GHRH receptor in the lab
- Phase 1 2 trials, 2 completed
- Phase 2 7 trials, 5 completed
- Phase 3 2 trials, 2 completed
- Approval in the USA since 2010
Show all 9 phase 2 and 3 trials on a timelineHide timeline
NCT01264497 · 55 participants, started Feb 2002, primary endpoint reached Nov 2002.
Registry entry ↗ · Results not yet in PubMed
SMART · NCT00257712 · 151 participants, started Feb 2006, primary endpoint reached Dec 2011.
Registry entry ↗ · Results: Baker et al., Archives of Neurology, 2012
NCT00675506 · 60 participants, started Jul 2008, primary endpoint reached Jan 2012.
Registry entry ↗ · Results: Makimura et al., Journal of Clinical Endocrinology & Metabolism, 2012
NCT02572323 · 73 participants, started Feb 2017, primary endpoint reached Oct 2023.
Registry entry ↗ · Results: Ellis et al., Journal of Infectious Diseases, 2025
NCT03150511 · 36 participants (planned), started Jun 2018, primary endpoint planned Dec 2027.
NCT03375788 · 51 participants, started Jan 2019, primary endpoint reached Jul 2024.
Registry entry ↗ · Results not yet in PubMed
NCT06554717 · 100 participants (planned), started Jul 2025, primary endpoint planned Jun 2028.
NCT00123253 · 412 participants, started Jun 2005, primary endpoint reached Nov 2006.
Registry entry ↗ · Results: Falutz et al., New England Journal of Medicine, 2007, Falutz et al., AIDS, 2008, Falutz et al., Journal of Clinical Endocrinology & Metabolism, 2010
NCT00608023 · 263 participants, started Aug 2007, primary endpoint reached Oct 2008.
Registry entry ↗ · Results: Falutz et al., Journal of Acquired Immune Deficiency Syndromes, 2010, Falutz et al., Journal of Clinical Endocrinology & Metabolism, 2010
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 25 Oct 2026. Phase 1: 2 trials on safety and pharmacokinetics, not shown as bars.
Side effects
The side effects are the ones you know from elevated GH: water retention, joint or muscle aches, occasionally tingling or numbness in the hands (carpal-tunnel-like). Per the US prescribing information, these complaints are usually transient or resolve after stopping. On top of that come injection-site reactions, which are among the most common side effects. The prescribing information also warns of glucose intolerance (an HbA1c of 6.5% or more occurred after 26 weeks in 5% on tesamorelin and 1% on placebo), so a look at blood sugar is worthwhile with longer use. After 26 weeks, IGF-1 was above the age-adjusted normal range in almost half of treated patients. 4% had hypersensitivity reactions such as itching, redness, flushing or rash.
Tolerability
Frequency in the phase 3 trials
Out of 100 participants per group, how many had the event in the first 26 weeks.
| Event | Placebo | Tesamorelin |
|---|---|---|
| Injection-site reaction11 | 6% | 17% |
| Joint pain11 | 11% | 13% |
| Muscle pain11 | 2% | 6% |
| Fluid retention in legs or arms11 | 2% | 6% |
| Tingling (paraesthesia)11 | 2% | 5% |
| HbA1c of 6.5% or more11 | 1% | 5% |
Rounded values from the US prescribing information (543 participants on Tesamorelin, 263 on placebo). Per that document fluid retention, joint pain and carpal tunnel complaints are mostly transient or resolve after stopping.11
Lifestyle
Tesamorelin works through your own GH rhythm, so a few things get a lot more out of it:
-
Sleep
The natural GH pulse comes in deep sleep. Good, sufficient sleep and the evening dose work together.
-
Spacing from meals
Insulin blunts GH release, so the evening dose is often given with some gap from the last big meal.
-
Resistance training
GH and IGF-1 do their best when the training stimulus is there.
-
Enough protein for recovery.

Anyone who sleeps badly anyway or eats large amounts right before bed gives away part of the effect.
Storage
The undissolved powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. Once dissolved, the solution goes into the fridge (2 to 8 degrees) and stays stable there for at least 4 to 6 months with barely any loss of potency, in practice considerably longer. The bacteriostatic water brings a preservative that keeps the dissolved form stable for longer.
Shelf life
How long it keeps
Robust, no fridge needed. Keeps for several months without trouble.
At least 4 to 6 months with barely any loss of potency. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial