What is the Tesa + Ipa Blend?
This blend combines tesamorelin, a particularly strong GHRH analog, with ipamorelin, a selective GHRP, in a 17mg vial (6mg tesa + 11mg ipa). You also find both individually in the lexicon. Tesamorelin is clinically known mainly for reducing visceral belly fat.
Comparison
One path or two
The blend next to the single compounds and the blend with CJC-1295, as stated in the TPD lexicon. Tap a card to open its entry.
Simplified: that two paths amplify each other has only been shown with older peptides in healthy adults, not with this blend. 8
How it works
As with the CP10 stack, two systems of the GH axis interlock: tesamorelin at the GHRH receptor, ipamorelin at the ghrelin receptor. Together this gives a strong GH pulse. The difference from CP10: tesamorelin is seen as the more potent GHRH analog with a particular focus on visceral fat.
The individual mechanisms are in the lexicon entries for tesamorelin and ipamorelin.
Where it acts
Where the two components act
Tap a point or a card. Colour = receptor, grey = observed in studies of the single compound.
- Pituitary
Two paths to growth hormone release, stronger together than alone (healthy men, older peptides)8
GHRHGhrelin - Belly fat
Tesamorelin: visceral fat -15.2 percent in 26 weeks, subcutaneous fat barely changed2
Observed in trials - Liver
Tesamorelin: 35 percent with normal liver fat after 12 months, placebo 4 percent4
Observed in trials - Gut
Ipamorelin after bowel surgery: first meal tolerated earlier, difference not significant7
Observed in trials
Targets in the ChEMBL database12
Compound CHEMBL1237026 (Tesamorelin), CHEMBL58547 (Ipamorelin): two recorded mechanisms, type of action on each card.
- Gene
- GHRHR
- UniProt
- Q02643
- ChEMBL
- CHEMBL2032
- Action
- Agonist, direct binding according to ChEMBL
- Gene
- GHSR
- UniProt
- Q92847
- ChEMBL
- CHEMBL4616
- Action
- Agonist according to studies, no mechanism recorded in ChEMBL

What you need
Supplies
2 things, numbered as in the picture
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
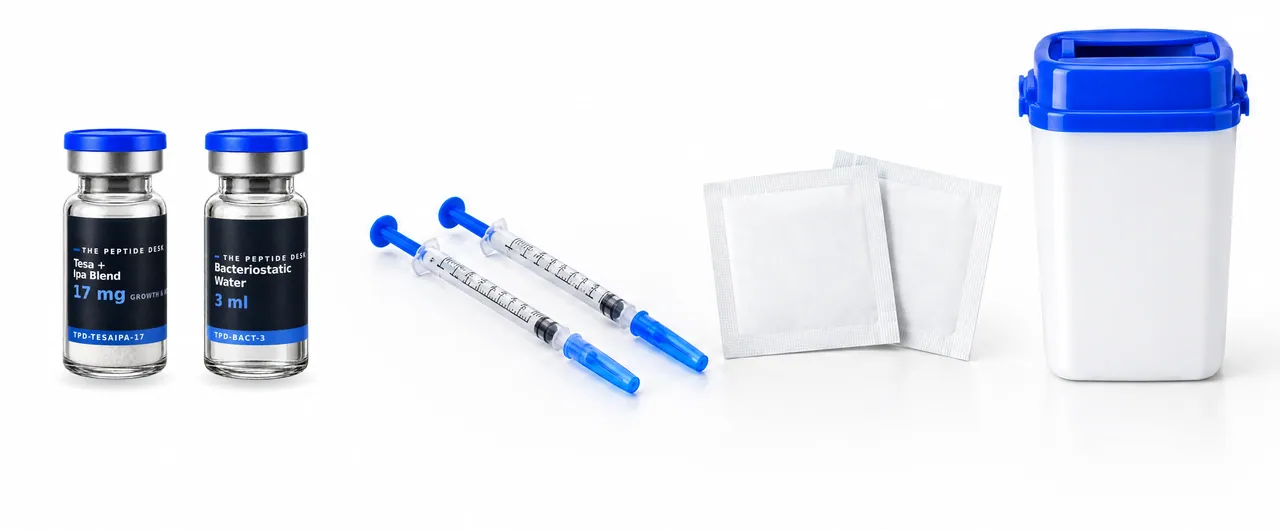
-
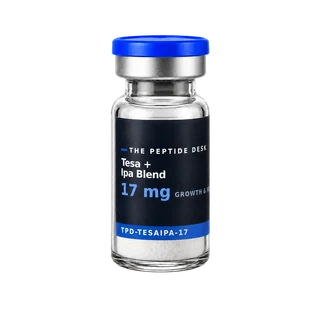
Blend vial
The blend vial (lyophilized powder, both compounds).
-
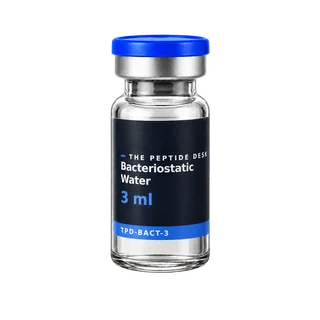
Water and supplies
Bacteriostatic water, U-100 insulin syringes, alcohol swabs.
Reconstitution
Use the peptide calculator. The values refer to the total amount (17mg). A 17mg vial with 1.7ml water gives 10mg total per ml: 3.1mg is then 31 units on the U-100 syringe, 1.5mg is 15 units. Just add the water to the vial and let it dissolve.
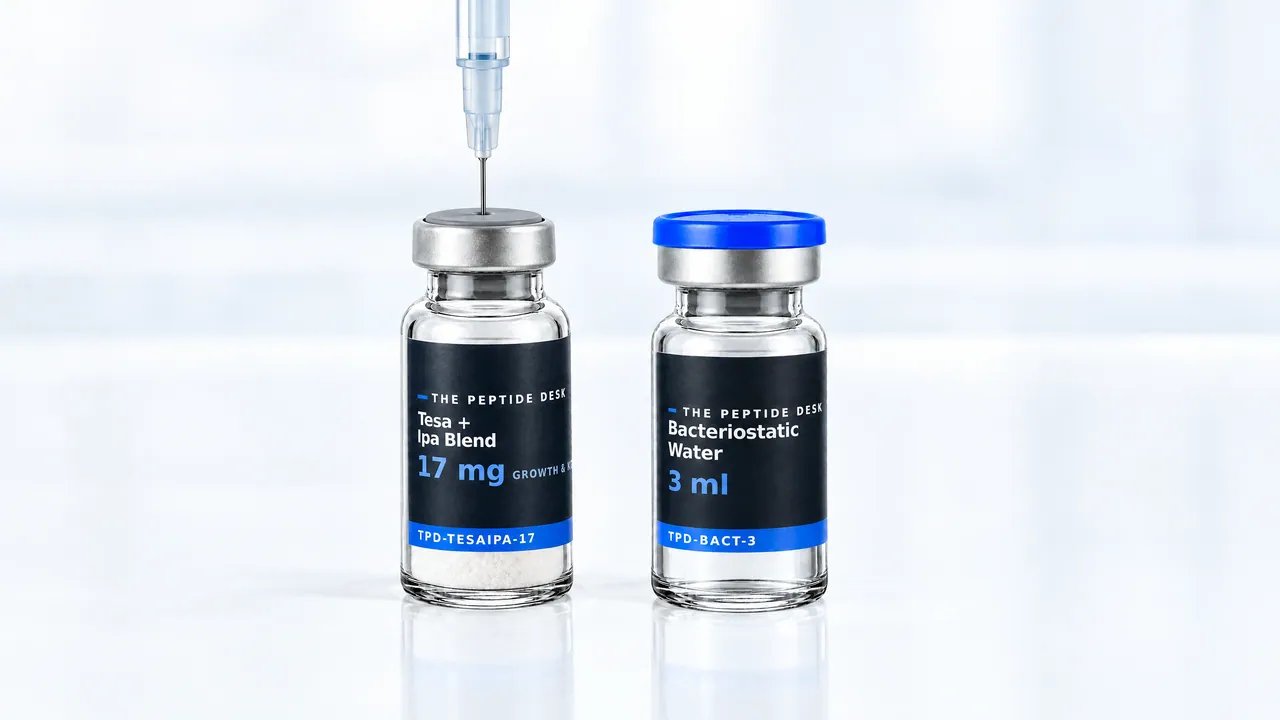
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
Injection
Subcutaneous, ideally fasted. Because of the tesamorelin share it is classically injected into the abdomen (keep about two finger-widths clear of the navel), as the tesamorelin prescribing information specifies. Disinfect the site, pinch a skin fold, insert at 90 degrees (45 degrees with little fat under the skin), rotate the spot on the abdomen every time.
What the research shows
The GHRH-analog pharmacology is studied in healthy people (Ionescu & Frohman, 2006). Tesamorelin is clinically documented for reducing visceral fat (details in the tesamorelin entry). For the fixed mix there is no separate study, the benefit derives from the individual compounds.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Visceral belly fat at 26 weeks23
Mean change in percent, by CT in people with HIV, tesamorelin alone
Values from the abstracts, studies with tesamorelin alone, not with the blend. IGF-1 rose by 81 percent in trial 1.
Normal liver fat after 12 months4
Share with less than 5 percent fat in the liver, 61 people with HIV and fatty liver
Liver fat fell by a relative 37 percent more than on placebo. Fasting glucose and HbA1c did not differ after 12 months.
Time to the first tolerated meal7
Median in hours after bowel surgery, phase 2, ipamorelin alone into a vein
The difference was not significant (p = 0.15). The trial tested ipamorelin for bowel paralysis, not as a growth hormone peptide.

Research status
Where the research stands
There is no study on the blend. Shown are registered trials on the single components: tesamorelin up to phase 3, ipamorelin up to phase 2. As of 26 Oct 2026. 11
- Preclinical Ipamorelin in cells, rats and pigs
- Phase 1 2 trials on components, 2 completed
- Phase 2 5 trials on components, 4 completed
- Phase 3 2 trials on components, 2 completed
- Approval not yet
Show all 8 trials on a timelineHide timeline
NCT00672074 · 117 participants, started Apr 2008, primary endpoint reached Dec 2009.
Registry entry ↗ · Results: Beck et al., International Journal of Colorectal Disease, 2014
NCT00675506 · 60 participants, started Jul 2008, primary endpoint reached Jan 2012.
Registry entry ↗ · Results not yet in PubMed
NCT01280344 · 320 participants, started Apr 2011, primary endpoint reached Jun 2013.
Registry entry ↗ · Results not yet in PubMed
NCT03375788 · 51 participants, started Jan 2019, primary endpoint reached Jul 2024.
Registry entry ↗ · Results not yet in PubMed
TRIUMPH · NCT06554717 · 100 participants (planned), started Jul 2025, primary endpoint planned Jun 2028.
NCT00123253 · 412 participants, started Jun 2005, primary endpoint reached Nov 2006.
Registry entry ↗ · Results: Falutz et al., New England Journal of Medicine, 2007
NCT00608023 · 263 participants, started Aug 2007, primary endpoint reached Oct 2008.
Registry entry ↗ · Results: Falutz et al., Journal of Acquired Immune Deficiency Syndromes, 2010
NCT02196831 · 61 participants, started Jul 2015, primary endpoint reached Jan 2019.
Registry entry ↗ · Results: Stanley et al., The Lancet HIV, 2019
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 26 Oct 2026. Phase 1: 2 trials on safety and pharmacokinetics, not shown as bars.
Side effects
- Water retention, tingling, joint stiffness at higher GH levels.
- Local reactions at the injection site.
Tolerability
Side effects of tesamorelin in phase 3
Out of 100 participants, how many had the event. Data on tesamorelin alone, 543 on the drug, 263 on placebo. There are no data on the blend.
| Event | Placebo | Tesamorelin alone |
|---|---|---|
| Injection-site reaction9 | 6% | 17% |
| Joint pain9 | 11% | 13% |
| Muscle pain9 | 2% | 6% |
| Fluid retention in legs or arms9 | 2% | 6% |
| Tingling (paraesthesia)9 | 2% | 5% |
| HbA1c of 6.5% or more9 | 1% | 5% |
Ipamorelin alone: after bowel surgery 87.5 percent had a side effect against 94.8 percent on placebo. Almost everyone has complaints after abdominal surgery, which cannot be transferred to injection under the skin.97
Storage
Before mixing the powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. After mixing, keep in the fridge (2 to 8 degrees), do not freeze. It stays good there for at least 4 to 6 months with barely any loss of potency, in practice considerably longer. Swirl or shake to mix, both are fine.
Shelf life
How long it keeps
Robust, no fridge needed.
At least 4 to 6 months with barely any loss of potency. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial