What is Tirzepatide?
Tirzepatide is a peptide you inject once a week. What makes it special: it binds two receptors at the same time, GIP and GLP-1. Pure GLP-1 compounds like semaglutide only hit one of them. That dual approach is exactly why Tirzepatide is regarded, in a research context, as the most potent member of the incretin class to date.
The half-life sits at roughly five days, so one shot a week keeps levels stable. It ships as a freeze-dried powder that you dissolve in bacteriostatic water before the first use.
Comparison
One, two or three receptors
Which receptors each compound targets, as stated in the TPD lexicon. Tap a card to open its entry.
Simplified: more receptors does not automatically mean better, each path also brings its own effects. 33
How it works
Both receptors pull several levers at once. The insulin response is boosted in a glucose-dependent way, the stomach empties more slowly and satiety signals in the brain get engaged. What most people notice day to day: the constant circling around food, the so-called food noise, gets much quieter.
Studies suggest the dual GIP/GLP-1 approach moves more on the metabolic side than GLP-1 alone. That does not mean more is automatically better. The body often responds fully at moderate amounts.
- GLP-1 Slower gastric emptying · More satiety in the brain
- GIP Insulin response boosted
Where it acts
Two receptors, several organs
Tap a point or a card. Colour = receptor, grey = effect seen in trials.
- Brain
Lower food intake (shown in mice)5
GLP-1GIP - Stomach
Gastric emptying delayed, less so after repeated doses6
GLP-1 - Pancreas
Insulin boosted in a glucose-dependent way, HbA1c clearly lower in trials8
GLP-1GIP - Fat tissue
Fat cells carry only the GIP receptor and respond through it (cell assay)5
GIP - Liver
MASH resolved more often in a phase 2 trial31
Observed in trials - Heart
Fewer heart failure events with preserved ejection fraction and obesity30
Observed in trials
Targets in the ChEMBL database33
Compound CHEMBL4297839: two recorded mechanisms, all agonist with direct binding to the human receptor.
- Gene
- GIPR
- UniProt
- P48546
- ChEMBL
- CHEMBL4383
- Action
- Agonist, direct binding
- Gene
- GLP1R
- UniProt
- P43220
- ChEMBL
- CHEMBL1784
- Action
- Agonist, direct binding
What you need
Before you start, have everything ready. The list is short:
Supplies
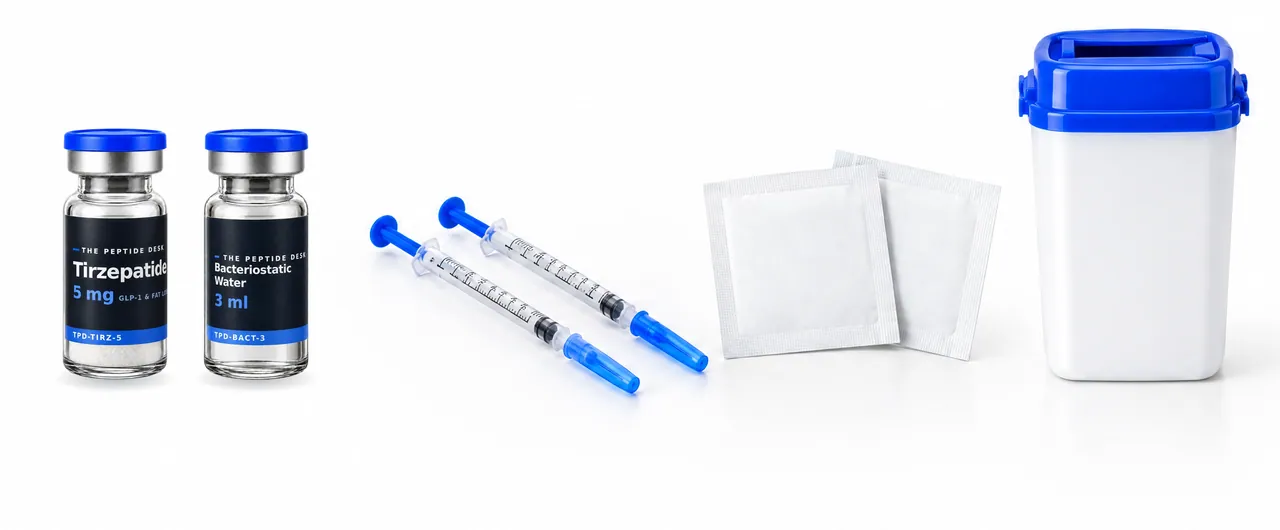
5 things, numbered as in the picture
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-
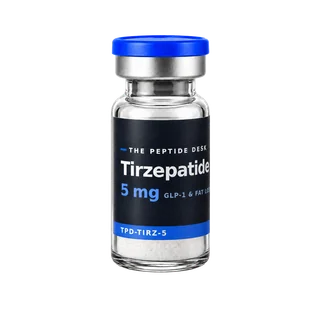
Tirzepatide vial
The Tirzepatide vial with the freeze-dried powder
-
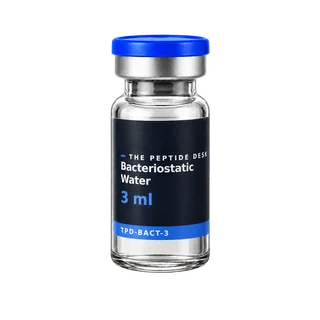
Bacteriostatic water
Bacteriostatic water to dissolve it
-
U-100 insulin syringes
U-100 insulin syringes for the injection (they also work for drawing the water, you just draw more often; a larger syringe is faster but not a must)
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin
-
Sharps container
A sealable sharps container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
With everything clean and in one place, the rest is straightforward.
Reconstitution
The powder is dissolved in bacteriostatic water. How much water you add sets the concentration and therefore how many units you later draw on the insulin syringe for your dose.
Use the peptide calculator for exactly this: pick your vial size and the water volume to instantly see the concentration and the units per dose. Roughly: less water means higher concentration and fewer units. For large vials from 30mg up, more water is worth it, otherwise the dose gets tiny and hard to read.
When dissolving, just add the bac water and let the powder dissolve. It does not matter if the water hits the powder directly. Swirling or shaking are both fine.
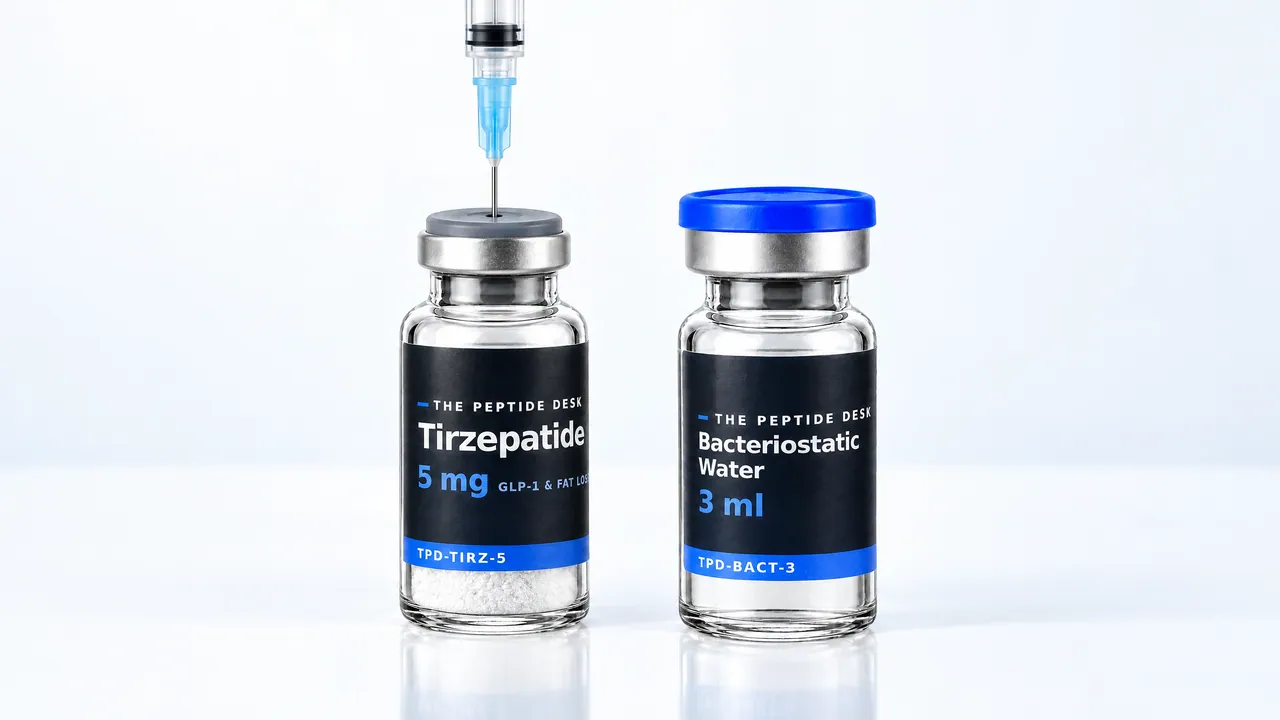
Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
The injection is subcutaneous, into the fat layer under the skin. Common spots are the abdomen (keep about two finger-widths clear of the navel), the front and the inner side of the thigh, or the back of the upper arm.
The short version:
Injection
Where and at what angle
Pick a spot or switch the angle. Subcutaneous means: into the fat layer, not the muscle.
Rotate the spot each time, never the same one twice in a row.
Rule of thumb: where there is more fat under the skin, insert straight at 90 degrees. In lean people with little fat, 45 degrees, so the needle stays in the fat layer. Simplified diagram.
-
Clean the spot with an alcohol swab and let it dry
-
Pinch up a small fold of skin
-
Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
-
Inject slowly, wait a moment, then withdraw
-
Put the needle straight into the sharps container
Rotate the site each time so the tissue does not get irritated. Never the same spot twice in a row.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
In the large registration studies, Tirzepatide showed clear effects on blood-sugar markers (HbA1c) and body weight through its dual incretin mechanism, rising with the dose across the tested steps. The data base is the weight studies from the SURMOUNT series and the diabetes studies from the SURPASS series.
The individual studies with links are in the source block below.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Body weight at the end of the trial22223
Mean change in percent per trial
Values for all participants as randomised (treatment-regimen estimand), as stated in the abstracts. SURMOUNT-2 had no arm with the lowest dose. In SURMOUNT-3 the change counts from randomisation, after everyone had already lost at least 5 percent with diet and exercise. The trials are not directly comparable.
Long-term blood sugar HbA1c at 40 weeks9
Change in percentage points, SURPASS-2, comparison with semaglutide in type 2 diabetes
Values as stated in the abstract, highest study dose versus semaglutide. The other dose levels of the trial are not shown here.
Body weight over 88 weeks24
Mean change from baseline in percent, SURMOUNT-4 with 670 randomised participants
Tirzepatide continued: Week 0 0.0%, Week 36 -20.9%, Week 88 -25.3%. Placebo from week 36: Week 0 0.0%, Week 36 -20.9%, Week 88 -9.9%.
Everyone received Tirzepatide at the maximum tolerated dose for 36 weeks (mean -20.9%). Then participants were randomised: continue Tirzepatide or switch to placebo. From week 36 to 88 the placebo group regained 14.0 percent on average, the other group lost a further 5.5 percent. Only the time points from the abstract are shown.
Body weight after 72 weeks25
Head-to-head trial, obesity without type 2 diabetes, 751 participants
Least-squares means from the abstract. Waist circumference also fell more with Tirzepatide (-18.4 versus -13.0 cm). Both groups mainly had gastrointestinal effects, mostly during the step-up phase.
Liver biopsy after 52 weeks31
Share of participants, phase 2 trial SYNERGY-NASH with 190 participants
Participants with biopsy-confirmed MASH and moderate to severe fibrosis. Missing biopsies were imputed as described in the abstract. A phase 2 trial, the authors call for larger and longer trials.
Research status
Where the research stands
From the first cell assays to approval: the developer's registered trials testing Tirzepatide on its own, with status, participants and results. As of 25 Oct 2026. 32
- Preclinical Cell assays and mice
- Phase 1 20 trials, 18 completed
- Phase 2 5 trials, 4 completed
- Phase 3 29 trials, 23 completed
- Approval since 2022
Show all 34 phase 2 and 3 trials on a timelineHide timeline
NCT03131687 · 318 participants, started May 2017, primary endpoint reached Aug 2018.
Registry entry ↗ · Results: Frias et al., The Lancet, 2018
NCT03311724 · 111 participants, started Oct 2017, primary endpoint reached Apr 2018.
Registry entry ↗ · Results: Frias et al., Diabetes, Obesity and Metabolism, 2020
SYNERGY-NASH · NCT04166773 · 190 participants, started Nov 2019, primary endpoint reached Dec 2023.
Registry entry ↗ · Results: Loomba et al., New England Journal of Medicine, 2024
TREASURE-CKD · NCT05536804 · 134 participants, started Feb 2023, primary endpoint reached Jul 2026.
Registry entry ↗ · Results not yet in PubMed
NCT06037252 · 414 participants, started Sept 2023, primary endpoint planned Jan 2026.
SURPASS-4 · NCT03730662 · 2,002 participants, started Nov 2018, primary endpoint reached Jan 2021.
Registry entry ↗ · Results: Del Prato et al., The Lancet, 2021
SURPASS J-combo · NCT03861039 · 443 participants, started Mar 2019, primary endpoint reached Jan 2021.
Registry entry ↗ · Results: Kadowaki et al., The Lancet Diabetes & Endocrinology, 2022
SURPASS-3 · NCT03882970 · 1,444 participants, started Apr 2019, primary endpoint reached Dec 2020.
Registry entry ↗ · Results: Ludvik et al., The Lancet, 2021
SURPASS J-mono · NCT03861052 · 636 participants, started May 2019, primary endpoint reached Mar 2021.
Registry entry ↗ · Results: Inagaki et al., The Lancet Diabetes & Endocrinology, 2022
SURPASS-1 · NCT03954834 · 478 participants, started Jun 2019, primary endpoint reached Oct 2020.
Registry entry ↗ · Results: Rosenstock et al., The Lancet, 2021
SURPASS-2 · NCT03987919 · 1,879 participants, started Jul 2019, primary endpoint reached Jan 2021.
Registry entry ↗ · Results: Frías et al., New England Journal of Medicine, 2021
SURPASS-5 · NCT04039503 · 475 participants, started Aug 2019, primary endpoint reached Dec 2020.
Registry entry ↗ · Results: Dahl et al., JAMA, 2022
SURMOUNT-1 · NCT04184622 · 2,539 participants, started Dec 2019, primary endpoint reached Apr 2022.
Registry entry ↗ · Results: Jastreboff et al., New England Journal of Medicine, 2022, Jastreboff et al., New England Journal of Medicine, 2025
SURPASS-AP-Combo · NCT04093752 · 917 participants, started Dec 2019, primary endpoint reached Nov 2021.
Registry entry ↗ · Results: Gao et al., Nature Medicine, 2023
SURPASS-CVOT · NCT04255433 · 13,299 participants, started May 2020, primary endpoint reached Jun 2025.
Registry entry ↗ · Results: Nicholls et al., New England Journal of Medicine, 2025
SURPASS-6 · NCT04537923 · 1,428 participants, started Oct 2020, primary endpoint reached Oct 2022.
Registry entry ↗ · Results: Rosenstock et al., JAMA, 2023
SURMOUNT-2 · NCT04657003 · 938 participants, started Mar 2021, primary endpoint reached Mar 2023.
Registry entry ↗ · Results: Garvey et al., The Lancet, 2023
SURMOUNT-4 · NCT04660643 · 783 participants, started Mar 2021, primary endpoint reached Apr 2023.
Registry entry ↗ · Results: Aronne et al., JAMA, 2024
SURMOUNT-3 · NCT04657016 · 579 participants, started Mar 2021, primary endpoint reached Apr 2023.
Registry entry ↗ · Results: Wadden et al., Nature Medicine, 2023
SUMMIT · NCT04847557 · 731 participants, started Apr 2021, primary endpoint reached Jul 2024.
Registry entry ↗ · Results: Packer et al., New England Journal of Medicine, 2025
SURMOUNT-J · NCT04844918 · 267 participants, started May 2021, primary endpoint reached Jun 2023.
Registry entry ↗ · Results: Kadowaki et al., The Lancet Diabetes & Endocrinology, 2025
SURMOUNT-CN · NCT05024032 · 210 participants, started Sept 2021, primary endpoint reached Dec 2022.
Registry entry ↗ · Results: Zhao et al., JAMA, 2024
SURPASS-PEDS · NCT05260021 · 99 participants, started Apr 2022, primary endpoint reached Jul 2024.
Registry entry ↗ · Results: Hannon et al., The Lancet, 2025
SURMOUNT-OSA · NCT05412004 · 469 participants, started Jun 2022, primary endpoint reached Mar 2024.
Registry entry ↗ · Results: Malhotra et al., New England Journal of Medicine, 2024
SURMOUNT-MMO · NCT05556512 · 15,374 participants, started Oct 2022, primary endpoint planned Oct 2027.
SURPASS-CN-INS · NCT05691712 · 257 participants, started Feb 2023, primary endpoint reached Jul 2024.
Registry entry ↗ · Results: Guo et al., The Lancet Diabetes & Endocrinology, 2025
SURMOUNT-5 · NCT05822830 · 751 participants, started Apr 2023, primary endpoint reached Nov 2024.
Registry entry ↗ · Results: Aronne et al., New England Journal of Medicine, 2025
SURPASS-CN-MONO · NCT05963022 · 206 participants, started Aug 2023, primary endpoint reached Oct 2024.
Registry entry ↗ · Results: Yin et al., Med, 2026
SURMOUNT-MAINTAIN · NCT06047548 · 441 participants, started Sept 2023, primary endpoint reached Jan 2026.
Registry entry ↗ · Results: Horn et al., The Lancet, 2026
NCT06075667 · 160 participants, started Oct 2023, primary endpoint planned Jun 2026.
SURMOUNT-ADOLESCENTS-2 · NCT06439277 · 300 participants (planned), started Jun 2024, primary endpoint planned Oct 2027.
SURPASS-T1D-1 · NCT06914895 · 905 participants (planned), started Apr 2025, primary endpoint planned Nov 2026.
SURPASS-T1D-2 · NCT06962280 · 465 participants (planned), started May 2025, primary endpoint planned Nov 2026.
ADVANCE-SURMOUNT-KIDS · NCT07817875 · 150 participants (planned), started Sept 2026, primary endpoint planned Dec 2029.
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 25 Oct 2026. Phase 1: 20 trials on safety and pharmacokinetics, not shown as bars.
Side effects
The most common hit is the gastrointestinal tract: nausea, fullness, sometimes diarrhoea or constipation. It shows up mainly at the start and after each dose increase. It usually settles once the body has adjusted. That is exactly what the slow ramp is for. Wanting to go too high too fast is the most common avoidable mistake.
Tolerability
Frequency in the phase 2 trial
Out of 100 participants per group, how many had the event over 26 weeks.
| Event | Placebo | Level 1 (lowest) | Level 2 | Level 3 | Level 4 (highest, 15 mg) |
|---|---|---|---|---|---|
| Gastrointestinal effects1 | 10% | 23% | 33% | 51% | 66% |
| Decreased appetite1 | 2% | 4% | 20% | 26% | 19% |
Values from the abstract of the phase 2 trial in type 2 diabetes (nausea, diarrhoea and vomiting combined). A later trial showed that a lower start and smaller steps when increasing went along with fewer side effects. In SURMOUNT-1 4.3 to 7.1 percent stopped because of side effects, 2.6 percent on placebo.172
Lifestyle
Tirzepatide takes the hunger away, the rest is on you. A few things get more out of the research phase and keep you healthy:
-
Enough protein
If you eat little, make the little you eat protein-rich, or you lose muscle along with fat.
-
Drink enough
With low appetite you often drink less without noticing. The risk of dehydration then goes up.
-
Resistance training
Keeps muscle mass while the weight comes off.
-
Eat slowly
With delayed gastric emptying you fill up faster, big portions sit heavy.

Alcohol and very fatty meals make the nausea noticeably worse, especially early on.
Storage
The undissolved powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. Once dissolved, the solution goes into the fridge (2 to 8 degrees) and stays stable there for at least 4 to 6 months with barely any loss of potency, in practice considerably longer. The bacteriostatic water brings a preservative that keeps the dissolved form stable for longer.
Shelf life
How long it keeps
Robust, no fridge needed. Keeps for several months without trouble.
At least 4 to 6 months with barely any loss of potency. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial