What is Retatrutide?
Retatrutide (development name LY3437943) is the third generation of incretin research. Where semaglutide hits one receptor and Tirzepatide two, Retatrutide acts on three at once: GLP-1, GIP and additionally glucagon. That third path, the glucagon receptor, is what is new about it and the reason Retatrutide is regarded, in research, as the most potent member of the class so far.
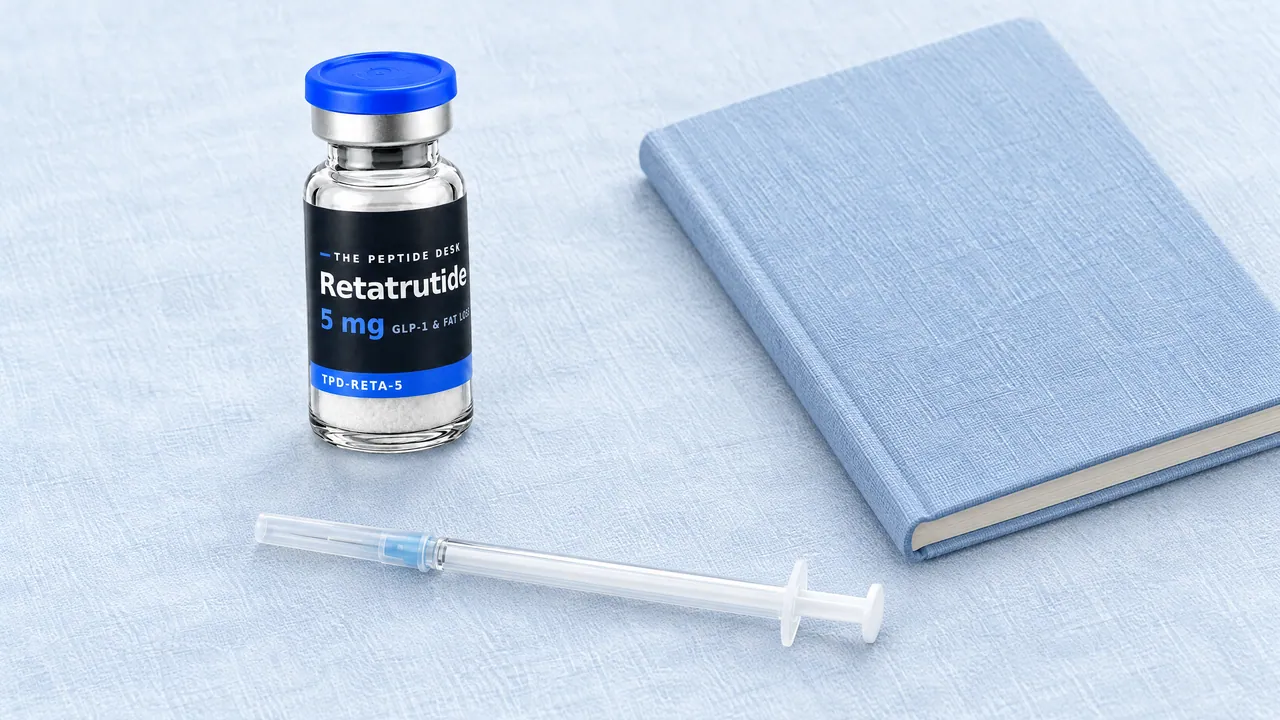
It is injected once a week and the half-life sits at roughly six days. Like the others it comes as a freeze-dried powder you dissolve in bacteriostatic water before the first use.
Comparison
One, two or three receptors
Which receptors each compound targets, as stated in the TPD lexicon. Tap a card to open its entry.
Simplified: more receptors does not automatically mean better, each path also brings its own effects. 1012
How it works
You know GLP-1 and GIP from Tirzepatide: they boost the insulin response, slow gastric emptying and dampen appetite. The glucagon receptor is the new addition in Retatrutide. Glucagon sounds counterintuitive at first because it can raise blood sugar, but in concert with the other two paths it mainly increases energy expenditure and fat breakdown, especially in the liver.
In studies this liver effect was particularly clear: liver fat dropped by over 80 percent at the higher doses. Studies suggest the three-path combination moves more on weight and metabolism than the earlier one- or two-receptor approaches.
- GLP-1 Appetite dampened · Gastric emptying slowed
- GIP Insulin response boosted
- Glucagon Energy expenditure up · Fat breakdown, especially in the liver
Where it acts
Three receptors, several organs
Tap a point or a card. Colour = receptor, grey = effect seen in trials.
- Brain
Lower food intake, appetite dampened10
GLP-1GIP - Stomach
Gastric emptying slowed9
GLP-1 - Pancreas
Blood sugar lowered, HbA1c clearly lower in trials6
GLP-1GIP - Liver
Fat breakdown, liver fat dropped sharply in studies7
Glucagon - Energy balance
Energy expenditure increased (shown in animal models)10
Glucagon - Heart
Heart rate rose slightly, dose-dependent5
Observed in trials
Targets in the ChEMBL database12
Compound CHEMBL5095485: three recorded mechanisms, all agonist with direct binding to the human receptor.
- Gene
- GLP1R
- UniProt
- P43220
- ChEMBL
- CHEMBL1784
- Action
- Agonist, direct binding
- Gene
- GIPR
- UniProt
- P48546
- ChEMBL
- CHEMBL4383
- Action
- Agonist, direct binding
- Gene
- GCGR
- UniProt
- P47871
- ChEMBL
- CHEMBL1985
- Action
- Agonist, direct binding
What you need
Before you start, have everything ready. The list is short:
Supplies
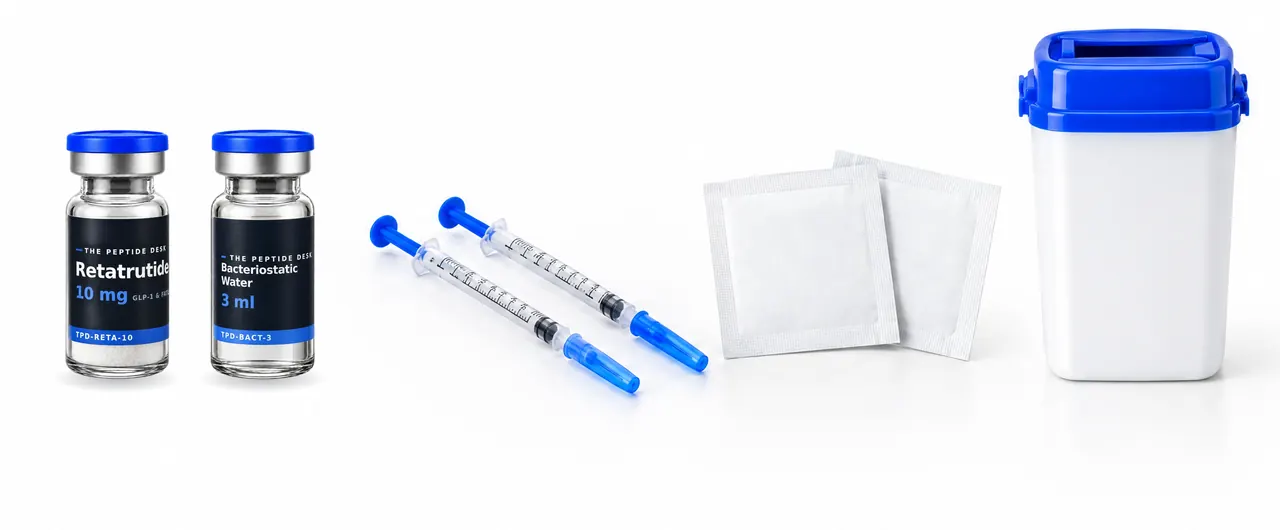
5 things, numbered as in the picture
Tick off what you already have. Vial and BAC water are our real shop photos at the same size.
-

Retatrutide vial
The Retatrutide vial with the freeze-dried powder
-
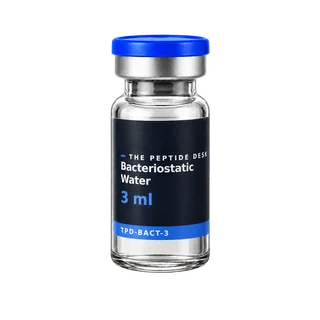
Bacteriostatic water
Bacteriostatic water to dissolve it
-
U-100 insulin syringes
U-100 insulin syringes for the injection (they also work for drawing the water, you just draw more often; a larger syringe is faster but not a must)
-
Alcohol swabs
Alcohol swabs for the vial cap and the skin
-
Sharps container
A sealable sharps container for used needles
As an Amazon associate we earn from qualifying purchases. Links open Amazon - no extra cost for you.
With everything clean and in one place, the rest is straightforward.
Reconstitution
The powder is dissolved in bacteriostatic water. How much water you add sets the concentration and therefore how many units you later draw on the insulin syringe for your dose.
That is exactly what the peptide calculator is for: pick your vial size and the water volume to instantly see the concentration and the units per dose. Roughly: less water means higher concentration and fewer units. For large vials from 30mg up, more water is worth it, otherwise the dose gets tiny and hard to read.
When dissolving, just add the bac water and let the powder dissolve. It does not matter if the water hits the powder directly. Swirling or shaking are both fine.

Step by step
Dissolving the powder
Four steps, the same for every vial size.
- 1Wipe the cap
Clean the rubber stopper with an alcohol swab.
- 2Add BAC water
Just add it, it does not matter if it hits the powder directly.
- 3Swirl or shake
Until everything has dissolved, both are fine.
- 4Draw up
With the U-100 insulin syringe.
Injection
The injection is subcutaneous, into the fat layer under the skin. Common spots are the abdomen (keep about two finger-widths clear of the navel), the front and the inner side of the thigh, or the back of the upper arm.
The short version:
Injection
Where and at what angle
Pick a spot or switch the angle. Subcutaneous means: into the fat layer, not the muscle.
Rotate the spot each time, never the same one twice in a row.
Rule of thumb: where there is more fat under the skin, insert straight at 90 degrees. In lean people with little fat, 45 degrees, so the needle stays in the fat layer. Simplified diagram.
-
Clean the spot with an alcohol swab and let it dry
-
Pinch up a small fold of skin
-
Insert the needle: at 90 degrees where there is more fat under the skin, at 45 degrees in lean people with little fat
-
Inject slowly, wait a moment, then withdraw
-
Put the needle straight into the sharps container
Rotate the site each time so the tissue does not get irritated. Never the same spot twice in a row.
Dosing
Dosing
Dosing, titration and syringe
Loading the dosing information …
- Getting started and stepping up, drawn as a staircase
- Units on the U-100 syringe for every step
- How long one vial lasts
What the research shows
Retatrutide is still in clinical research. The first results from the phase 3 programme are now out. In the large TRIUMPH-1 trial (obesity without diabetes) body weight fell by 25.0 percent on average after 80 weeks at the highest study dose, by 3.9 percent on placebo. In TRIUMPH-2 with type 2 diabetes it was 18.8 versus 5.1 percent. In TRANSCEND-T2D-1 blood sugar (HbA1c) also dropped clearly in type 2 diabetes.
The phase 2 data were already clear: in the obesity study the highest dose (12mg) led to roughly 24 percent weight reduction at 48 weeks. In a liver substudy liver fat fell by over 80 percent at the higher doses. Further phase 3 trials on heart, kidney and liver run until 2029 and 2030.
The individual studies with links are in the source block below.
Study results
What the trials measured
Interactive: switch tabs, tap points, show or hide arms. Arms are named relative to each other, no dosing advice.
Body weight over 48 weeks5
Mean change in percent, phase 2 trial with 338 participants
Placebo: Week 0 0.0%, Week 24 -1.6%, Week 48 -2.1%. Level 1 (lowest): Week 0 0.0%, Week 24 -7.2%, Week 48 -8.7%. Level 2: Week 0 0.0%, Week 24 -12.9%, Week 48 -17.1%. Level 3: Week 0 0.0%, Week 24 -17.3%, Week 48 -22.8%. Level 4 (highest, 12 mg): Week 0 0.0%, Week 24 -17.5%, Week 48 -24.2%.
Only the time points reported in the abstract are shown (weeks 0, 24 and 48), the lines connect them straight. Levels 2 and 3 each combine two groups with a different starting dose.
Body weight at the end of the trial123
Mean change in percent per trial
Values for all participants as randomised (treatment-regimen estimand), as stated in the abstracts. The trials differ in population and duration and are not directly comparable.
Liver fat at 24 weeks7
Relative change in liver fat, substudy with 98 participants (MASLD)
Measured by MRI as the fat fraction of the liver. The substudy ran within the phase 2 obesity trial.
Research status
Where the research stands
From the first cell assays to the large phase 3 programme: every registered trial with status, participants and results. As of 25 Oct 2026. 11

- Preclinical Cell assays and mice
- Phase 1 15 trials, 14 completed
- Phase 2 3 trials, 3 completed
- Phase 3 14 trials, 5 completed
- Approval not yet
Show all 17 phase 2 and 3 trials on a timelineHide timeline
NCT04881760 · 338 participants, started May 2021, primary endpoint reached May 2022.
Registry entry ↗ · Results: Jastreboff et al., New England Journal of Medicine, 2023, Sanyal et al., Nature Medicine, 2024
NCT04867785 · 281 participants, started May 2021, primary endpoint reached Jul 2022.
Registry entry ↗ · Results: Rosenstock et al., The Lancet, 2023
NCT05936151 · 146 participants, started Jul 2023, primary endpoint reached Oct 2025.
Registry entry ↗ · Results not yet in PubMed
TRIUMPH-3 · NCT05882045 · 1,946 participants, started May 2023, primary endpoint reached Apr 2026.
Registry entry ↗ · Results not yet in PubMed
TRIUMPH-1 · NCT05929066 · 2,335 participants, started Jul 2023, primary endpoint reached Apr 2026.
Registry entry ↗ · Results: Jastreboff et al., New England Journal of Medicine, 2026, Grunstein et al., New England Journal of Medicine, 2026
TRIUMPH-2 · NCT05929079 · 1,152 participants, started Jul 2023, primary endpoint reached Jun 2026.
Registry entry ↗ · Results: Bellido et al., The Lancet, 2026, Grunstein et al., New England Journal of Medicine, 2026
TRIUMPH-4 · NCT05931367 · 445 participants, started Aug 2023, primary endpoint reached Nov 2025.
Registry entry ↗ · Results not yet in PubMed
TRANSCEND-T2D-2 · NCT06260722 · 1,250 participants (planned), started Feb 2024, primary endpoint planned Aug 2026.
TRANSCEND-T2D-3 · NCT06297603 · 320 participants (planned), started Mar 2024, primary endpoint planned Oct 2026.
TRANSCEND-T2D-1 · NCT06354660 · 537 participants, started Apr 2024, primary endpoint reached Jan 2026.
Registry entry ↗ · Results: Bajaj et al., The Lancet, 2026
TRIUMPH-OUTCOMES · NCT06383390 · 10,000 participants (planned), started Apr 2024, primary endpoint planned Feb 2029.
TRIUMPH-5 · NCT06662383 · 800 participants (planned), started Nov 2024, primary endpoint planned Nov 2026.
TRIUMPH-6 · NCT06859268 · 643 participants (planned), started Mar 2025, primary endpoint planned Apr 2028.
TRIUMPH-7 · NCT07035093 · 586 participants (planned), started May 2025, primary endpoint planned Sept 2027.
SYNERGY-Outcomes · NCT07165028 · 4,500 participants (planned), started Oct 2025, primary endpoint planned Aug 2030. Tests several agents.
TRIUMPH-8 · NCT07232719 · 250 participants (planned), started Nov 2025, primary endpoint planned Jul 2027.
TRIUMPH-9 · NCT07357415 · 600 participants (planned), started Jan 2026, primary endpoint planned Oct 2028.
Bar: start to primary endpoint (planned for running trials). Green = completed, blue = progress until 25 Oct 2026. Phase 1: 15 trials on safety and pharmacokinetics, not shown as bars.
Side effects
Like the other incretins, the most common effects are gastrointestinal: nausea, fullness, sometimes diarrhoea or constipation, mainly at the start and after each dose increase. Through the glucagon path, studies additionally noted a slight rise in heart rate. In the phase 3 trial TRIUMPH-2 abnormal skin sensations (dysaesthesia) and low blood pressure also occurred more often than on placebo. These effects are dose-dependent and one more reason to ease in slowly and not go up too fast.
Tolerability
Frequency in TRIUMPH-2
Out of 100 participants per group, how many had the event over 80 weeks.
| Event | Placebo | Lowest study dose | Middle study dose | Highest study dose (12 mg) |
|---|---|---|---|---|
| Nausea2 | 8% | 14% | 21% | 28% |
| Diarrhoea2 | 13% | 27% | 34% | 34% |
| Abnormal skin sensations (dysaesthesia)2 | 1% | 4% | 6% | 7% |
| Stopped due to side effects2 | 5% | 4% | 12% | 8% |
Rounded values from the trial abstract (obesity with type 2 diabetes). In the phase 2 trial heart rate rose in a dose-dependent way, most around week 24, less afterwards.25
Lifestyle
Retatrutide takes the hunger away, the rest is on you. A few things get more out of the research phase and keep you healthy:
-
Enough protein
If you eat little, make the little you eat protein-rich, or you lose muscle along with fat.
-
Drink enough
With low appetite you often drink less without noticing. The risk of dehydration then goes up.
-
Resistance training
Keeps muscle mass while the weight comes off.
-
Eat slowly
With delayed gastric emptying you fill up faster, big portions sit heavy.

Alcohol and very fatty meals make the nausea noticeably worse, especially early on.
Storage
The undissolved powder is robust, normal room temperature (around 20 to 25 degrees) is fine, ideally kept in the dark. Once dissolved, the solution goes into the fridge (2 to 8 degrees) and stays stable there for at least 4 to 6 months with barely any loss of potency. The bacteriostatic water brings a preservative that keeps the dissolved form stable for longer.
Shelf life
How long it keeps
Robust, no fridge needed. Keeps for several months without trouble.
At least 4 to 6 months with barely any loss of potency. The bacteriostatic water brings a preservative.
- Keep it dark
- Dissolved: 2 to 8 degrees
- Note the mixing date on the vial